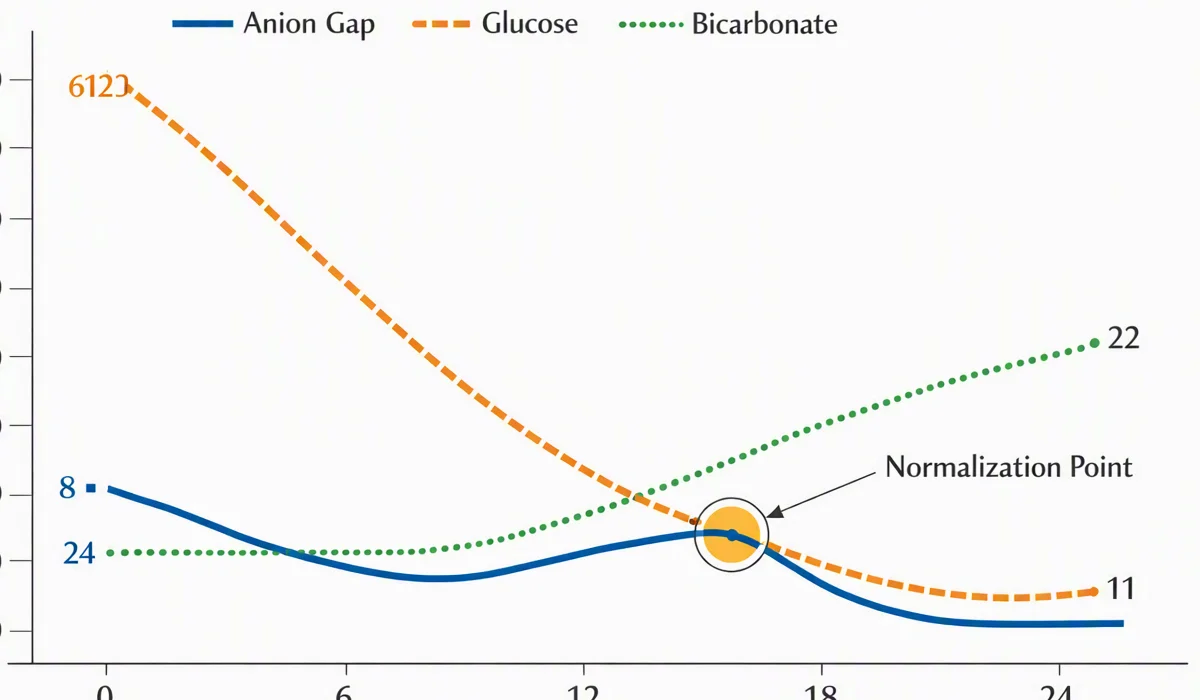
What Is the Anion Gap?
The anion gap is a calculated value that helps healthcare providers interpret electrolytes and assess acid-base balance. It is not a lab test by itself. Instead, it is a diagnostic aid derived from routine blood test results, usually from a standard serum chemistry or electrolyte panel.
At its core, the anion gap approximates the difference between the major measured positive and negative ions in the blood. Because some ions are not directly measured, the result can offer clues about anion concentration and the presence of unmeasured anions. That makes it especially valuable in the evaluation of an acid-base disorder, particularly when metabolic acidosis is suspected.
An anion gap calculator is simply a medical calculator that performs this calculation for you once the relevant lab values are entered. The result can support clinical interpretation, but it should always be considered alongside symptoms, the full metabolic panel, and other laboratory findings.
What Lab Values Does an Anion Gap Calculator Need?
To work out the anion gap, an anion gap calculator typically requires three core lab values: sodium, chloride, and bicarbonate. They are often listed as serum sodium, serum chloride, and serum bicarbonate on a serum chemistry report.
This set of measurements come from routine blood chemistry testing and are often included in a basic metabolic panel or comprehensive metabolic panel. Most of the time, the calculator uses the same numbers you would see on the lab report, so there is no extra test beyond the standard blood draw.
This is what each input contributes:
- Sodium: the main measured cation used in the calculation. Chloride: the primary measured anion that is subtracted from sodium. Bicarbonate: a key buffer that reflects acid-base status and is also subtracted in the standard formula.
Since these are common measurements in a metabolic panel, the anion gap is easy to compute from everyday laboratory data. In simple terms, the calculator uses the values already available from a routine blood test, which makes it a quick way to assess electrolyte balance and possible disturbances in acid-base physiology.
How the Anion Gap Formula functions
The usual anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This computation uses the recorded ions existing in the blood, usually expressed in mEq/L. The formula reflects the fact that the body maintains electrical neutrality, meaning positively charged and negatively charged substances must balance. However, not all ions are measured in routine lab work.
That is why the anion gap is useful. It assists calculating the amount of electrically charged ions not directly covered in the basic lab set. These hidden components are often referred to as unmeasured anions. When the gap changes, it can suggest that something is affecting acid-base physiology or altering the ratio of measured and unmeasured substances.
A calculator makes this easier by performing the arithmetic instantly. Still, understanding the calculation formula matters because the result depends entirely on the correctness of the input values. If the sodium level, chloride level, or bicarbonate level is incorrect, the anion gap will also be inaccurate.
Some clinicians also follow a adjusted version of the formula that includes potassium, but the standard approach does not require it. The basic version is the one most commonly used in routine clinical interpretation.
How Albumin May Matter in Clinical Interpretation
Even though albumin is not part of the standard anion gap formula, it can noticeably affect how the result is interpreted. Albumin is a negatively charged protein and a major contributor to the https://penzu.com/p/8d5577689c9dee07 body’s overall electrical balance. When albumin is low, the anion gap may appear lower than expected even if a clinically important acid-base issue is present.
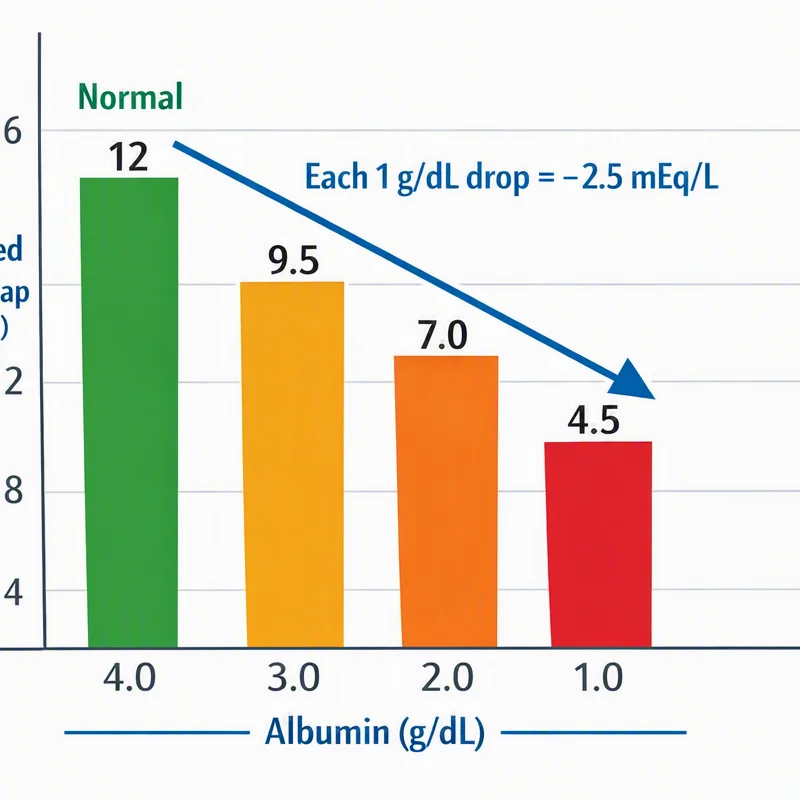
That is why hypoalbuminemia matters. If albumin is reduced, the measured anion gap can underestimate the true burden of unmeasured acids. In that situation, clinicians may consider an albumin-corrected anion gap to obtain a better estimate of the underlying problem.
The correction is not always required, but it becomes more relevant when the patient has low protein levels, liver disease, malnutrition, inflammation, or critical illness. In those situations, the usual normal range may not tell the full story.
For that reason, albumin is an important part of clinical interpretation even though it is not one of the three core inputs used by most anion gap calculators. A more complete assessment often includes the lab context, the overall electrolyte balance, and whether the patient may have a masked high anion gap due to low albumin.
What Results Are Considered Within Normal Limits or Abnormal
The normal anion gap varies somewhat with the laboratory as well as the analyzer in use, so the normal range can vary. Many labs report a usual range that is specific enough to guide interpretation but still slightly different from one system to another.
As a rule, a result is considered:
- Normal anion gap: within the lab’s stated reference range. High anion gap: higher than the normal range and often associated with added unmeasured acids. Low anion gap: below the normal range and less frequent, sometimes due to protein changes or measurement issues.
A high anion gap is often the more important clinically finding because it may point to a problem with acid handling, acid production, or acid clearance. A low value is usually interpreted more cautiously because it is less often a sign of a primary disease process.
It is important to compare the result with the lab-specific reference range and the full clinical picture. The same number may be interpreted differently depending on the patient’s sodium, chloride, bicarbonate, albumin, and overall condition. This is where the medical interpretation of the blood test matters more than the number alone.
Typical Reasons of a Increased Anion Gap
A elevated anion gap usually indicates a buildup of acidic compounds that are not directly measured in the standard lab panel. This result is frequently seen in metabolic acidosis, especially when the body is generating too much acid or cannot clear it effectively.
A few of the most common causes are:
- Lactic acidosis: happens when lactate accumulates, frequently in situations of poor oxygen flow, shock, severe illness, or intense physiologic stress. Ketoacidosis: develops when ketones build up, frequently in diabetes, prolonged fasting, or alcohol-related metabolic states. Renal failure: reduces the body’s ability to remove acid and can result in retention of unmeasured anions.
Such conditions can increase the gap because they add to the amount of acids not included among the standard measured ions. The result may help guide clinicians toward the correct diagnosis, but it does not identify the cause on its own. Additional testing and clinical context are needed to determine whether the issue is lactic acidosis, ketoacidosis, kidney failure, or another process.
In practice, the anion gap is one part of the broader evaluation of metabolic panel results. It helps sort the type of acidosis and determine whether the patient has a metabolic acidosis with an elevated gap or another acid-base pattern entirely.
Frequently Asked Questions
This section addresses common questions about the anion gap calculator, the required lab values, and how different panels change the result. These answers can help you use an electrolyte panel more confidently and see what the numbers mean.
Is Potassium Needed for the Calculation?
Usually, no. The standard formula for the anion gap uses sodium, chloride, and bicarbonate only. Potassium is included in some versions of the calculation, creating a modified anion gap, but that is not the most common method in routine clinical use. Most anion gap calculator tools rely on the standard formula unless they specifically say otherwise.
Can an Anion Gap Be Calculated from a Basic Metabolic Panel?
Yes. A basic metabolic panel usually includes the values needed for the calculation: sodium, chloride, and bicarbonate. A comprehensive metabolic panel also includes those same values, so either lab test can provide the data needed for anion gap calculation. If the report includes the key electrolytes, the calculator can use them right away.
Why Might the Anion Gap Be Low?
A low anion gap can happen for several reasons, including lab error, changes in chloride, or conditions such as multiple myeloma. Because low results are less common than high ones, they often prompt a careful review of the laboratory data and the patient’s overall condition. Low albumin can also contribute, so the result should be interpreted in light of other findings rather than in isolation.
What values are needed to calculate the anion gap?
You need three main lab values: serum sodium, serum chloride, and serum bicarbonate. An anion gap calculator uses those values to perform the standard calculation. In some cases, albumin may also be useful for interpretation, especially if the clinician is considering an albumin-corrected anion gap.
Does an anion gap calculator take into account potassium?
Most of the time, no. The common standard formula does not include potassium. A small number of calculators offer a adjusted anion gap that adds potassium, but that is not the common approach. If potassium is relevant, it is usually because the clinician wants a more specific interpretation rather than a basic screening value.
Can you get the anion gap from a basic metabolic panel?
Absolutely. A basic chemistry panel usually includes the necessary test results, so it can be used to determine the anion gap. A complete metabolic panel also works because it includes the same electrolyte measurements. As long as the lab test reports sodium, chloride, and bicarbonate, the calculation can be done.
Why is albumin important when interpreting the anion gap?
Albumin level matters because it serves as a major unmeasured anion. When albumin is reduced, especially in hypoalbuminemia, the calculated anion gap can seem incorrectly normal or low. Under those circumstances, an albumin-corrected anion gap may better reflect the true acid-base status and reveal a hidden high anion gap.
How does a high or decreased anion gap mean?
A elevated anion gap often points toward metabolic acidosis resulting from conditions such as lactic acidosis, ketoacidosis, or kidney failure. A low anion gap is relatively uncommon and may result from lab error, protein abnormalities, or changes in chloride. The result should always be understood using the full clinical picture and the laboratory’s normal range.