What Is Anion Gap?
The anion gap is a derived value used to assess electrolytes and the body’s acid-base balance. It measures the gap between the main measured cations and opposing ions in the blood, especially sodium and chloride, along with bicarbonate. Because some ions are not directly measured on a standard blood chemistry panel, the anion gap can help detect changes in anion concentration that may suggest a metabolic disorder or other acid-base disorder.
Clinicians often use the anion gap as a diagnostic indicator and a screening tool during patient evaluation. It does not provide a diagnosis by itself, but it can suggest that something is affecting serum levels and overall chemical balance. The key idea is simple: if the gap is elevated or lower than expected, the blood test results may need closer review in clinical interpretation.
At its core, the anion gap indicates the presence of unmeasured anions in the blood. In many cases, those unmeasured ions become more relevant when the body is dealing with an acid load, kidney problems, or shifts in proteins such as albumin.
Anion Gap Calculator Formula
An anion gap calculator usually uses a straightforward formula based on common laboratory values. The standard calculation is:
Anion gap = Serum sodium − (Serum chloride + Serum bicarbonate)
That calculation formula compares measured sodium relative to the sum of bicarbonate and chloride. The result helps show whether there may be an acid buildup or unusual ions affecting the blood. Because the formula relies on common test values, it is easy to apply once the values are available from a lab report.
Some labs and clinicians may use a modified version that includes potassium, but the sodium-based version is the most common in everyday practice. When using any anion gap calculator, it is important to understand which lab reference standard is being used so the result is interpreted correctly.
The formula is useful because it turns a few routine numbers into a useful medical assessment of electrolyte balance. A high or low result can suggest an electrolyte imbalance that needs attention, especially if the patient has symptoms or abnormal blood test results.
How to Compute Anion Gap In Steps
To carry out the calculation, begin with the values from the blood chemistry panel:
- Serum sodium Serum chloride Serum bicarbonate
Then follow the formula:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Here is a quick example. If serum sodium is 140 mEq/L, serum chloride is 104 mEq/L, and serum bicarbonate is 24 mEq/L, the calculation is:
140 − (104 + 24) = 140 − 128 = 12 mEq/L
That value may fall within the expected normal range depending on the laboratory measurement method. The units are usually expressed in mEq/L. Because different instruments and lab methods can produce small variations in results, the exact reference range should always be checked against the reporting laboratory.
When reviewing the result, the number alone is not enough. The broader interpretive context is important, including symptoms, medications, kidney function, and whether there is evidence of metabolic acidosis or another acid-base disorder.
Normal Anion Gap Range and Measurement Units
The usual range for anion gap depends on the laboratory and the analytical method used. Many labs report a benchmark range that is roughly in the single-digit range to teen range when measured in mEq/L. However, there is no single universal cutoff that applies to every lab because test values can vary based on technology and calibration.
That is why it is best to interpret the result alongside the lab’s own local reference. A value that appears borderline in one setting may be normal in another. Also, different formulas may produce slightly different totals, which can affect how a result is categorized.
For practical use, the anion gap should be viewed as a trend as well as a single number. Repeated changes in the result may be more meaningful than one isolated value, especially if the patient’s serum levels are shifting over time.
Why a Raised Anion Gap Indicates
A raised anion gap often suggests that extra acids are building up in the body, which can point to an acid-base imbalance. In this setting, the blood contains additional unmeasured anions that are not captured by the routine electrolyte panel. This is why the result is such a useful clinical clue in a medical assessment.
Frequent causes include lactic acidosis, where lactic acid rises during poor tissue oxygenation, shock, or severe illness, and acid buildup from ketones, where ketones accumulate, often in diabetes, starvation, or alcohol-related states. Both conditions create an acid load that raises the gap.
A raised result may also be seen in kidney failure, because the kidneys may not clear acids effectively. In some cases, a toxic exposure can raise the anion gap as well. The pattern should always be matched with symptoms, other lab data, and the overall clinical interpretation.
In short, a high anion gap does not tell you the exact cause, but it does alert clinicians to a likely metabolic problem affecting acid handling or electrolyte balance.
What a Low Anion Gap Indicates
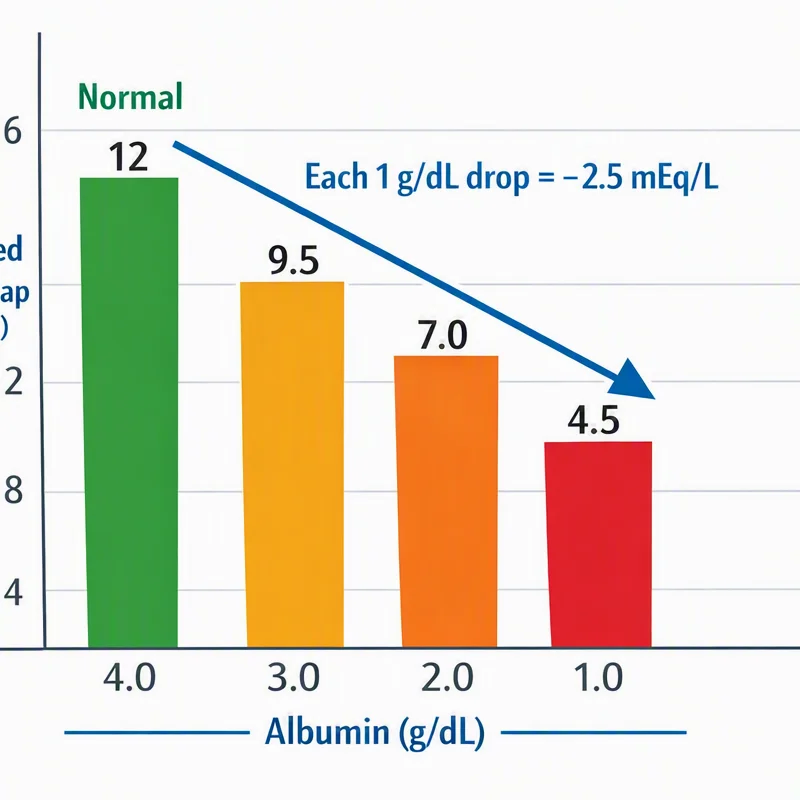
A decreased anion gap is rarer than a high one, but it can still matter. One key cause is hypoalbuminemia, because albumin is a negatively charged protein that helps form the measured balance of ions. When albumin falls, the gap may fall even if the underlying acid-base status has not changed much.
Another possible explanation is https://blogfreely.net/galimewfjy/raw-vs-revised-anion-gap-whats-the-difference lab error. Since the calculation depends on three distinct measurements, any mistake in serum sodium, serum chloride, or serum bicarbonate can affect the final result. That is why a very unexpected low value often deserves repeat testing or a careful review of the original blood test results.
Occasionally, a low result may reflect unusual proteins or other analytical issues. Because the number can be influenced by so many variables, it should be interpreted as part of the full clinical interpretation rather than as a standalone finding.
Adjusted Anion Gap & Albumin Correction
As albumin creates a strong effect on the anion gap, clinicians may use an albumin correction to estimate a corrected anion gap. This is especially important in hypoalbuminemia, where the unadjusted value may look artificially low.
The aim of the adjustment is to adjust for low negatively charged protein levels. Put differently, if albumin is reduced, the measured gap may overlook the presence of excess acids. A corrected value can therefore offer a clearer picture of the patient’s real acid-base status.
Several correction methods exist, and the exact approach may differ by clinician or institution. The important point is that the adjustment should be used when albumin is abnormal, because it improves the usefulness of the anion gap as a screening tool and facilitates more accurate patient evaluation.
Albumin correction does not replace the original result. Rather it offers context and helps reduce missing a significant acid-base imbalance when albumin is low.
Common Causes of an Abnormal Anion Gap
An abnormal anion gap may reflect several different disorders, so the result must be linked to the rest of the case. Common causes of a high value include:
- Metabolic acidosis with acid accumulation Lactic acidosis Ketoacidosis Renal failure Toxin ingestion
In addition, certain substances can alter the calculation or resemble an abnormal pattern. Some toxic exposures alter the expected balance of measured and unmeasured ions. A careful review of medications, exposures, and symptoms is part of accurate clinical interpretation.
A low value may stem from hypoalbuminemia, lab error, or other testing issues. Since the anion gap is derived from a blood chemistry panel, the quality of the input values directly changes the final result. That makes it a helpful but indirect marker in a broader medical assessment.
Whenever the result is abnormal, clinicians should ask whether the pattern fits the patient’s condition, whether the value is consistent with the lab’s reference range, and whether repeat testing is needed.
How to Interpret Results Safely
The safest way to interpret an anion gap is to go beyond the number itself. The result is part of a larger picture that includes the patient’s symptoms, other laboratory data, and the suspected cause of any acid-base balance problem. A single value does not constitute a diagnosis.
First, confirm the number against the reporting lab’s normal range and reference range. Then assess whether the patient has evidence of metabolic acidosis, kidney dysfunction, infection, diabetes complications, or a possible toxin ingestion. If albumin is low, consider a corrected anion gap before drawing conclusions.
It is equally important to remember that the anion gap is a diagnostic sign, not a complete explanation. It can suggest a range of problems, but additional testing may be required to identify the precise cause. Such testing may include repeat chemistry tests, blood gas testing, lactate measurement, ketones, kidney function studies, or toxicology evaluation.
Practically speaking, use the anion gap as a organized part of the medical interpretation of unusual blood test results. This method helps to reduce missed abnormalities and promotes better care.
Frequently Asked Questions
What formula is used for anion gap?
The usual anion gap equation equals serum sodium minus the sum of serum chloride and serum bicarbonate. Expressed mathematically, it is: Anion gap = sodium − (chloride + bicarbonate). Many anion gap calculator resources use the exact formula.
What is a normal anion gap value?
The typical range is determined by the laboratory and its reference interval, but many values fall in the single-digit range to low teens when reported in mEq/L. Be sure to compare the result with the lab’s own lab reference rather than relying on one universal cutoff.
Why might an anion gap be high?
A high anion gap typically indicates more acid or unmeasured anions may be present. Common causes include lactic acidosis, ketoacidosis, renal failure, and particular types of toxin ingestion. It is commonly an indication of metabolic acidosis or another acid-base problem.
Can a low anion gap be serious?
Certainly, although it is not as common. A reduced anion gap may stem from low albumin, testing error, or other issues. It may be benign in some cases, but it can also signal an issue that calls for further testing, especially if other blood test results are abnormal.
Should albumin be used to correct the anion gap?
Indeed, albumin should be taken into account when interpreting the result, especially if albumin is low. Albumin correction can provide a more accurate corrected anion gap and help avoid missing a hidden acid-base problem. This is particularly useful in low albumin and during broader clinical assessment.