What Is a Combined Acid–Base Disorder?
A complex acid–base disorder occurs when more than one mechanism is affecting acid-base balance at the same point. Instead of having a single straightforward pattern, the blood shows indications of several simultaneous changes. This is significant because a patient may appear acidotic, alkalotic, or even nearly normal on paper while still having a serious underlying problem.
The most frequent pairings involve metabolic acidosis along with a additional process such as respiratory alkalosis. Clinically, this means one condition is reducing bicarbonate or increasing acid load, while another is driving down carbon dioxide through overbreathing. The outcome can be misleading unless you use a systematic diagnostic approach and interpret the full clinical picture.
A combined acid-base imbalance is not just a lab finding. It often indicates a serious metabolic abnormality, respiratory compensation that is too strong or insufficient, or an independent problem affecting the lungs and kidneys at the same time. Because of that, result review should always include serum chemistry, blood gas analysis, and the clinical context.
What Can an Elevated Anion Gap Indicate?
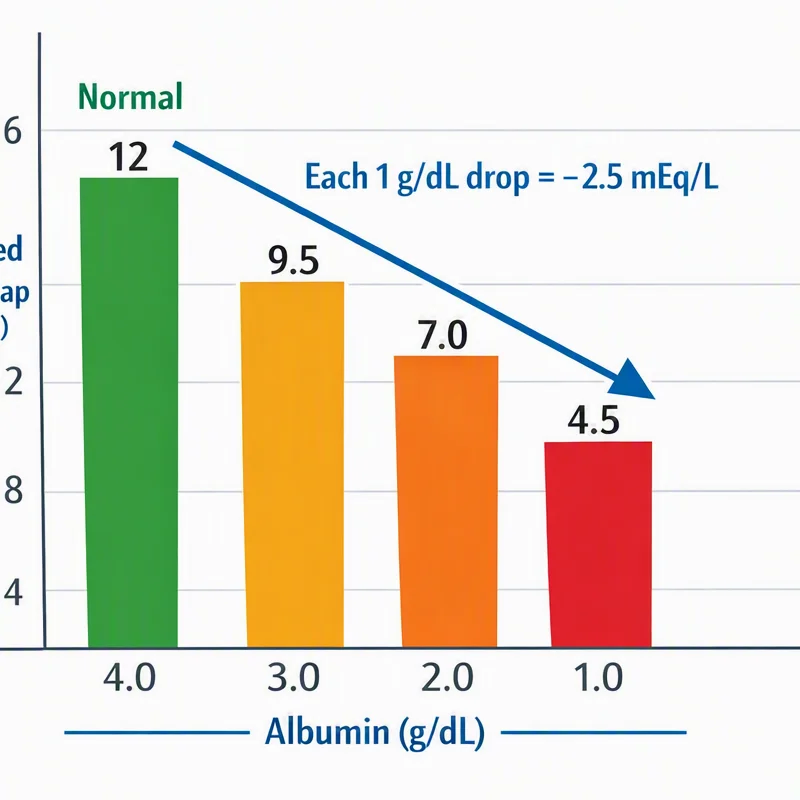
The anion gap is a derived value used to spot imbalances in electrolytes and acid-base regulation. It measures the difference between measured cations and measured anions in the serum, and it provides a clue about the presence of unmeasured anions in the units for anion gap bloodstream. When the elevated anion gap is present, it usually suggests that extra acids are building up.
An increased anion gap is most closely connected with high anion gap metabolic acidosis. In this scenario, bicarbonate is used up while acids build up, leaving behind negatively charged byproducts that are not directly measured on a standard panel. These may come from lactic acid, ketones, toxins, or impaired renal function.
Understanding the anion gap helps refine the differential diagnosis. It does not tell you the exact cause by itself, but it often indicates that the body is dealing with a specific type of acid loading or loss of acid excretion. That is why the anion gap is such a valuable part of laboratory interpretation.
How the Anion Gap Calculator Helps Interpretation
An Anion Gap Calculator streamlines the anion gap formula more straightforward to apply and helps reduce mistakes during quick assessment. The calculation typically uses serum sodium, serum chloride, and serum bicarbonate. Because these values are often already available on a routine metabolic panel, the calculator turns raw serum chemistry into a more useful result.
The classic formula is: sodium minus the sum of chloride and bicarbonate. That calculated value is the anion gap. A higher number suggests the presence of extra unmeasured anions and may indicate a high anion gap metabolic acidosis. The calculator can also help you spot whether the pattern suggests a single disorder or hints at a mixed acid-base disorder.
Using an Anion Gap Calculator is valuable because the result alone is not enough. You still need to compare it with the blood gas, the pH, the pCO2, and the patient’s symptoms. In other words, the calculator aids clinical reasoning, but it does not replace it. The best use is as part of a larger diagnostic approach that includes compensation analysis and an underlying cause review.
Frequent Causes of Mixed Acid-Base Imbalances With Elevated Anion Gap
A number of conditions can produce a mixed acid-base disorder with an elevated anion gap. Among the most common are lactic acidosis, ketoacidosis, and renal failure. Every one can create a high-gap metabolic acidosis, and each one can also occur along with another process such as alkalosis from breathing changes or strong respiratory compensation that is greater than expected.
Lactic acidosis occurs when tissues are deprived of adequate oxygen or when cells cannot process oxygen normally. The result is excess lactate production and acid buildup. It is often seen in serious illness, inadequate blood flow, seizures, or significant metabolic stress. If the patient is also hyperventilating, a respiratory alkalemia may also be present and make the pH less clearly abnormal.
Ketoacidosis happens when ketone production goes up, most often in diabetes that is not controlled, prolonged fasting, or alcohol-related metabolic stress. The ketoacids increase the anion gap and lower bicarbonate. If the person is ventilating quickly from pain, anxiety, infection, or sepsis, the blood gas may show a second disorder on top of the acidosis.
Renal failure can also lead to retention of acids that are normally excreted by the kidneys. As kidney function worsens, unseen acids accumulate and the serum anion gap may rise. This can happen progressively or suddenly, and it often requires thorough review to patterns of electrolyte disturbance and the full serum chemistry profile.
Identifying a Mixed Acid-Base Disorder in Lab Results
The main step in recognizing a mixed acid-base disorder is not just noticing an abnormal number. You need to analyze the arterial blood gas, including pH and pCO2, along with the chemistry panel. This combination shows you whether the body’s response is adequate or whether two separate processes are happening simultaneously.
The blood gas can show a low pH with low bicarbonate, which fits metabolic acidosis. But if the pCO2 is lower than expected, there may also be respiratory alkalosis. This is where the idea of a mixed disorder becomes important. The pH alone may not reveal the full story, especially if compensation is masking one component.
The delta gap is an additional helpful concept. It compares the rise in anion gap with the fall in bicarbonate. If the changes do not match expected patterns, a mixed process may be present. For example, a very high anion gap with only mild bicarbonate reduction may suggest an additional metabolic alkalosis. Likewise, an unexpectedly low pCO2 may point to superimposed respiratory alkalosis rather than simple compensation.
In everyday interpretation, abnormal labs should raise questions like: Is the pH acidemic or alkalemic? Is the pCO2 moving in the direction you would expect? Does the anion gap fit the degree of bicarbonate loss? This approach helps identify a straightforward pattern from a more complex metabolic disturbance.
Sequential Process to Reading Findings
A structured approach makes interpretation much more straightforward. Initially, review the pH to identify whether the patient is acidemic, alkalemic, or approximately normal. Then, establish whether the primary process looks of metabolic origin or respiratory. After that, review the serum anion gap to see whether there is evidence of high anion gap metabolic acidosis. This stepwise method provides a useful foundation for laboratory interpretation.
Next, use Winter's formula to estimate the expected respiratory compensation for metabolic acidosis. If the measured pCO2 is significantly higher than expected, there may be an coexisting respiratory acidosis. If the pCO2 is well below than expected, respiratory alkalosis may be present. This remains one of the crucial steps in identifying a mixed acid-base disorder.
Finally, assess whether the observed pattern fits the expected physiology. True compensation is the body’s expected response to a primary disorder, but compensation has boundaries. When the blood gas does not fit the expected pattern, it suggests more than one process. That is often the hint that the patient has an underlying cause requiring urgent attention.
A practical rule: if the anion gap is elevated and the pCO2 does not match the expected compensatory response, think past a single diagnosis and look for a second acid-base process.
Cases of Increased Anion Gap Mixed Conditions
One common example is someone with sepsis who develops lactic acidosis. The infection drives poor tissue perfusion and lactate buildup, causing high anion gap metabolic acidosis. Meanwhile, the patient may hyperventilate from fever, pain, or systemic stress, producing respiratory alkalosis. The blood gas can show a pH that is not as low as expected because the two disorders partially offset each other.
Another example involves toxic alcohols. These substances can generate acids that raise the anion gap, leading to severe metabolic acidosis. If the patient is also breathing rapidly due to physiologic stress, agitation, or central nervous system effects, a mixed pattern may appear. The result is a high-risk clinical scenario that requires prompt recognition.
Salicylate poisoning is a classic mixed disorder. It often causes respiratory alkalosis early because the toxic exposure stimulates the respiratory center. Later, a high anion gap metabolic acidosis develops as acid metabolites accumulate. The combination can produce a deceptively near-normal pH, which is why blood gas analysis and serum chemistry must be reviewed together.
These cases show why laboratory interpretation matters. A patient can be severely ill even when one number seems only mildly abnormal. The anion gap formula, pH, pCO2, and clinical presentation all need to be interpreted together to identify the correct diagnosis.
When to Obtain Urgent Healthcare Evaluation
Specific findings should require prompt medical evaluation, particularly when they appear alongside an raised anion gap. Concerning lab values such as a markedly reduced bicarbonate, markedly abnormal pH, or severely elevated serum anion gap may indicate a potentially fatal metabolic disturbance. These results need urgent clinical attention rather than routine follow-up.
Patient symptoms matter just as much as lab results. Mental status changes, confusion, extreme weakness, rapid breathing, chest discomfort, or inability to stay awake can all signal a serious acid-base disorder. If the patient is not protecting the airway or cannot provide a reliable history, the urgency increases.
Shock is another major warning sign. Poor perfusion can worsen lactic acidosis and rapidly destabilize the acid-base status. In that setting, the elevated anion gap may reflect a serious underlying cause such as sepsis, toxic ingestion, or organ failure. Immediate evaluation is needed because these conditions can progress quickly.
In short, a mixed acid-base disorder with a high anion gap is not something to ignore. It can represent a serious electrolyte disorder or systemic illness that needs prompt diagnosis and treatment.
Frequently Asked Questions
What is considered an elevated anion gap?
An elevated anion gap is a increased result on an anion gap calculation using serum sodium, serum chloride, and serum bicarbonate. The exact cutoff can vary by laboratory because reference ranges differ, but a clearly increased value suggests excess unmeasured anions and raises concern for high anion gap metabolic acidosis. Always interpret the number with the rest of the blood gas and serum chemistry results.
How does a mixed acid-base disorder differ from a simple disorder?
A simple disorder has one primary acid-base problem with an appropriate compensatory response. A mixed acid-base disorder has multiple separate processes happening at the same time, such as metabolic acidosis plus respiratory alkalosis. The clue is often that the pH, pCO2, and bicarbonate do not fit the expected pattern for a single disorder.
Can a patient have both metabolic acidosis and respiratory alkalosis at the same time?
Absolutely. This is a classic mixed acid-base condition. It can happen in sepsis, salicylate poisoning, liver disease, or other situations where the body is producing acid while also increasing ventilation. In these cases, the pCO2 may be less than predicted for routine compensation, and the pH may appear less abnormal than the severity of illness would suggest.
What conditions most commonly cause a high anion gap?
Frequent causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions all produce or hold onto acids that increase the anion gap. The best differential diagnosis comes from pairing the anion gap with the arterial blood gas, clinical findings, and other laboratory interpretation clues.
How do you calculate and interpret the anion gap in lab results?
The anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Anion Gap Calculator can make that process faster and reduce calculation errors. Once you have the result, check it against the expected compensation using Winter's formula, review the pH and pCO2, and look for signs of a combined acid-base disorder. Interpretation works best when the calculated value is considered together with the patient’s symptoms and underlying cause rather than viewed alone.