What exactly is the Anion Gap?
The anion gap is a calculated value used to help interpret an electrolyte panel. It compares the main measured positively charged ions and negatively charged ions in the blood, especially sodium, chloride, and bicarbonate. Because routine testing does not measure every ion directly, the anion gap offers clinicians a useful snapshot of overall electrolyte imbalance and acid-base status.
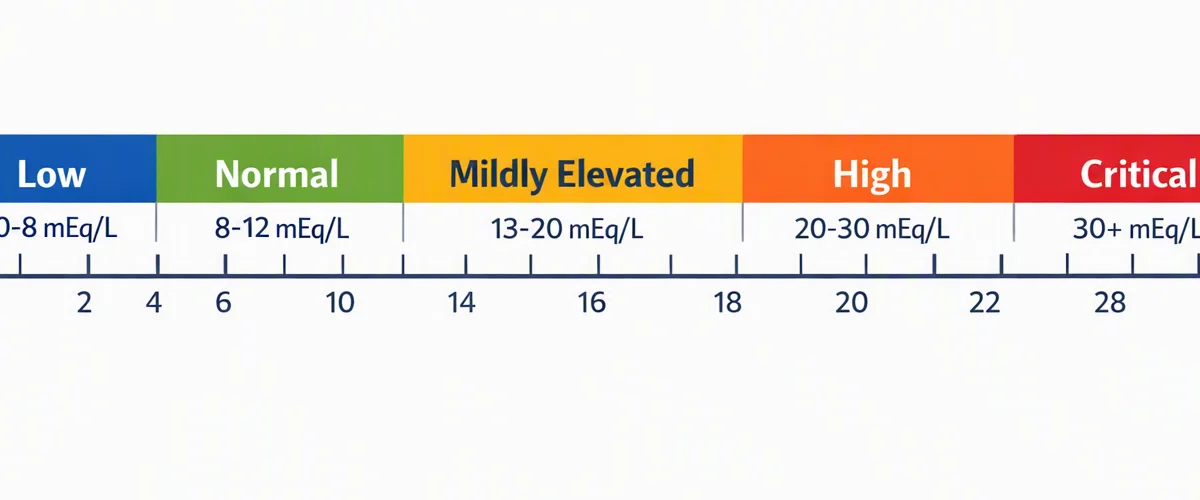
In simple terms, the gap reflects the difference between unmeasured cations and unmeasured anions. A normal reference interval suggests that measured and unmeasured ions are relatively balanced. A low anion gap can signal a lab issue, a change in serum albumin, or the presence of abnormal proteins in the bloodstream. For that reason careful lab interpretation matters. The Anion Gap Calculator aids in performing the gap calculation quickly and consistently, making it easier to compare a test result against the expected range.
Although the anion gap is not a standalone diagnosis, it remains an important screening test in routine chemistry. When it changes, clinicians often look at the broader pattern of the electrolyte panel rather than the number alone. That broader view is especially important when considering whether a result reflects true physiology or a laboratory artifact.
What Is Paraproteinemia?
Paraproteinemia describes the existence of an abnormal amount of a single type of protein in the blood, usually a monoclonal protein or M-protein. This protein is generated by a clone of abnormal plasma cells. Because these cells come from one line of replication, they make one dominant type of immunoglobulins or immunoglobulin fragment rather than the broad mix normally seen in healthy immune function.
Paraproteinemia is a descriptive term, not a diagnosis by itself. It is often seen in monoclonal gammopathy, which includes conditions such as MGUS (monoclonal gammopathy of undetermined significance), multiple myeloma, and Waldenström macroglobulinemia. In these disorders, the abnormal protein may circulate at low or high levels and may act as a plasma protein with unusual electrical properties.
The same monoclonal pattern can appear as a monoclonal spike on testing. The clinical significance depends on the amount of paraprotein burden, the presence of symptoms, and whether there is evidence of organ involvement. A monoclonal protein can be benign, premalignant, or malignant, but any unexpected shift in protein chemistry deserves attention.
How Paraproteins Affect the Anion Gap
Paraproteins can change the anion gap because of their protein charge. Certain cationic proteins carry a net positive charge at physiologic pH. When these proteins become more abundant, they can increase the amount of unmeasured cations in the blood. The result is often anion gap reduction, because the calculated gap shrinks as the chemistry panel tries to account for the ionic balance.
This effect is most notable when the abnormal protein behaves as a strongly charged paraprotein. In some cases, the charge characteristics of the monoclonal protein can push the gap lower even before other abnormalities become obvious. That makes the anion gap a potential diagnostic clue in patients with subtle disease.
Hypoalbuminemia can amplify the effect. Albumin is one of the main negatively charged proteins in the blood, so lower albumin reduces the anion gap on its own. When low albumin and cationic paraproteins occur together, the measured number can drop even more than expected. This is why the same low value may indicate more than one mechanism.
From a practical standpoint, the issue is not just whether the test result is low, but why it is low. A low value may represent true chemistry changes, a shift in protein balance, or a laboratory artifact. Distinguishing among these possibilities is the key to accurate interpretation.
How a Reduced Anion Gap Is Important
A low anion gap value is rarer than an elevated one, so it ought not be overlooked. In many cases, the first step is to run again the test and review whether the result fits the patient’s presentation. When the low value persists, it can point toward conditions such as paraproteinemia, electrolyte errors, or medication effects.
One reason it matters is that it may be an early indicator to a plasma cell disorder such as multiple myeloma. The finding does not diagnose the disease, but it can raise suspicion when combined with anemia, bone pain, kidney dysfunction, or other abnormal labs. In the proper context, the anion gap becomes part of the broader case for follow-up evaluation.
It is also important because a low value may be overlooked as meaningless if the clinician is not aware of charge effects. Yet a low result can reveal a hidden issue with proteins, especially if the patient has a suspected monoclonal gammopathy. That is why a thorough review of the chemistry profile and protein studies is essential.
A low anion gap is not a diagnosis, but it can be a useful clue when viewed alongside protein studies, albumin, and the full electrolyte picture.
How to Understand Results with an Anion Gap Calculator
An Anion Gap Calculator helps standardize the interpretation of the test result. It takes values from the electrolyte panel to determine the gap and compare it with the expected reference range. This makes it easier to notice when the result is unexpectedly low and may need further review.
Many calculators also offer albumin correction, which is most useful when serum albumin is low. Because albumin reduces the anion gap when it decreases, an uncorrected result can miss the true underlying gap. Correcting for albumin helps differentiate a low value caused by hypoalbuminemia from one caused by cationic paraproteins or another process.
For best interpretation, the calculator should be used with the full chemistry context: sodium, chloride, and bicarbonate, along with serum albumin and the patient’s clinical status. That combination enhances lab interpretation and helps identify whether the test https://anion-gap-calculation.com/case-studies/dka.html result reflects a routine variation, a laboratory artifact, or a medically significant abnormality.
The calculator is especially helpful when trends matter. A single number may be less informative than repeated values showing persistent anion gap reduction. When the gap remains low across different draws and the albumin correction does not fully explain it, further evaluation becomes more urgent.
Common Causes of a Low Anion Gap Other Than Paraproteinemia
Paraproteinemia is merely one possible cause of a reduced anion gap. Actually, more common causes should usually be considered first. One of the commonest is hypoalbuminemia, since albumin is a key unmeasured anion. When albumin drops, the gap can decline as well.
Additional causes include medication or toxin effects. Lithium can lower the gap because it is an unmeasured cation. Bromide exposure can affect with some lab methods and create misleading chloride readings. Hypermagnesemia may also add to the effect by increasing nonmeasured cations. In each of these instances, the issue is not the same as paraproteinemia, even though the final number may look similar.
Laboratory artifact must always still remain on the list. A imperfect specimen, analytic interference, or unusual assay behavior can produce a spuriously low value. This is why a thorough review of the entire electrolyte panel, repeated testing when appropriate, and comparison with earlier results are essential parts of the workup.
Because the low anion gap has multiple causes, context matters. A low value in a person with normal albumin and no medication explanation may be more suggestive for a protein-related disorder than the same value in someone with clear hypoalbuminemia.
When to Suspect This Condition
Monoclonal gammopathy should be suspected when a low anion gap remains without a different clear explanation, especially if there are other signs of protein abnormalities. This is particularly relevant when the pattern suggests a monoclonal protein rather than a nonspecific change in total protein. The presence of a low gap can be a small hint that abnormal plasma cells are producing excess immunoglobulins or related fragments.
The standard follow-up evaluation includes serum protein electrophoresis, which can reveal a monoclonal spike. Immunofixation helps identify the type of protein involved, while free light chains can uncover light-chain disease or quantify clonal activity more precisely. In some cases, beta-2 microglobulin is also useful because it can help assess disease burden and prognosis in plasma cell disorders.
These tests do not take the place of the anion gap; they follow it. The low gap acts as a signal that the chemistry profile may be leading toward a protein abnormality. When the signal is ongoing and supported by the rest of the clinical picture, the case for a monoclonal gammopathy becomes stronger.
It is also important to remember that not every paraproteinemia means cancer. MGUS may be unchanged and asymptomatic, while multiple myeloma and Waldenström macroglobulinemia require more urgent assessment. The role of the anion gap is to prompt the next next step, not to determine the final diagnosis on its own.
Frequently Asked Questions
How can paraproteinemia reduce the anion gap?
Paraproteinemia can lower the anion gap because certain monoclonal proteins behave like cationic proteins. Their positive charge increases unmeasured cations in the blood, which can cause anion gap reduction. Put another way, the gap narrows because the measured sodium, chloride, and bicarbonate values no longer reflect the full charge balance. The effect is stronger when the paraprotein has a larger protein charge contribution.
Can a low anion gap be an early sign of multiple myeloma?
Yes, it can be an early diagnostic clue, but it is not specific for multiple myeloma. A low anion gap may be seen before other findings become obvious, especially if there is a sizable monoclonal protein. However, it can also occur for other reasons, including hypoalbuminemia and laboratory artifact. This is why a low value should prompt review of the full clinical picture rather than be treated as a diagnosis by itself.
Does hypoalbuminemia cause a low anion gap more often than paraproteinemia?
Yes, hypoalbuminemia is generally a more common cause of a low anion gap than paraproteinemia. Albumin is a major unmeasured anion, so when it falls, the gap usually falls too. Still, paraproteinemia matters because it can create a low gap through a different mechanism, especially when monoclonal gammopathy or multiple myeloma is present. The best interpretation uses both the raw value and albumin correction.
Which tests should come after a low anion gap result?
If the low gap persists, common follow-up tests include a repeat electrolyte panel, serum albumin, and protein studies. The next steps often include serum protein electrophoresis, immunofixation, and free light chains. Depending on the context, clinicians may also check beta-2 microglobulin. These tests help determine whether the low anion gap reflects a paraprotein issue, a medication effect, or another cause.
Can an Anion Gap Calculator account for albumin changes?
Indeed, an Anion Gap Calculator can be quite useful when albumin correction is included or used separately. This matters because albumin greatly affects the gap. Correcting for serum albumin improves lab interpretation and helps show whether the low result is explained by hypoalbuminemia or whether it remains suspicious for a monoclonal protein effect. It makes the calculator a helpful tool for reliable gap calculation and follow-up evaluation.