What Are the Anion Gap?
The anion gap is a derived result used anion gap clinical significance to aid in interpret serum electrolytes and understand a person’s acid base status. It compares the main measured cationic ions and negative ions in the blood, especially sodium and chloride, with bicarbonate factored in the balance. Because not every ion is directly measured, the anion gap offers a clue about unmeasured ions that may be present in the blood.
Clinicians often use this number as a diagnostic marker during a medical assessment when a person has an abnormal result on a blood chemistry panel or basic metabolic panel. It is not a standalone diagnosis. Instead, it helps shape clinical interpretation of a person’s electrolyte balance, possible systemic acidosis, and overall serum chemistry.
One reason the anion gap is so useful is that it can reveal a hidden change in anion concentration. If acids accumulate in the blood, the gap often rises. If certain proteins, measurement issues, or unusual conditions are present, the gap can fall. That is why the anion gap is both a screening test and an interpretive guide rather than a final answer by itself.
The anion Gap Formula and Tool Inputs
The anion gap formula is straightforward:
Anion gap = sodium - (chloride + bicarbonate)
Some labs and calculators may use an alternate formula depending on whether potassium is included, but the standard modern formula leaves potassium out. That is why an Anion Gap Calculator is useful: it can rapidly perform the gap calculation once the correct lab inputs are entered.
To use the calculator correctly, you need values from a blood test or basic metabolic panel. The typical inputs are:
- Sodium Chloride Bicarbonate
These are part of routine serum electrolytes and are usually reported in milliequivalents per liter. The calculator then returns a calculated value that can be compared with the lab’s reference interval.
Because the anion gap reflects the difference between measured cations and measured anions, it indirectly estimates the amount of unmeasured ions in the serum. That is why the result can support a broader medical assessment of acid-base disorders. It is a useful way to spot whether the blood chemistry pattern fits metabolic acidosis or another imbalance.
Stepwise: How to Calculate the Anion Gap
Here are the essential steps for calculation for finding the anion gap from common lab values:
- Locate the serum sodium value from the lab report. Identify the serum chloride value. Locate the bicarbonate value. Combine chloride and bicarbonate together. Take away that sum from sodium.
Example: When serum sodium is 140, serum chloride is 102, and bicarbonate is 24, then:
140 - (102 + 24) = 14
In this example, the anion gap is 14. Whether that is normal depends on the lab’s reference range, the testing method, and sometimes the patient’s albumin level. That is why, a single number should always be considered alongside the rest of the laboratory result.
When using an Anion Gap Calculator, make sure the inputs come from the same draw and the same blood chemistry panel. Mismatched values can distort the final interpretation. The calculator is only as accurate as the lab values entered into it, so reviewing the report carefully matters.
For practical use, the question is not only “What is the number?” but also “What does this number mean in context?” This context includes the rest of the serum chemistry, the patient’s symptoms, and whether there is evidence of metabolic acidosis or another acid-base disorder.
What Is a Typical Anion Gap?
A healthy range for the anion gap can vary by test facility because different instruments and methods create different reference range values. In many settings, the normal anion gap is located in a relatively narrow interval, but the exact cutoff should always be taken from the lab report.
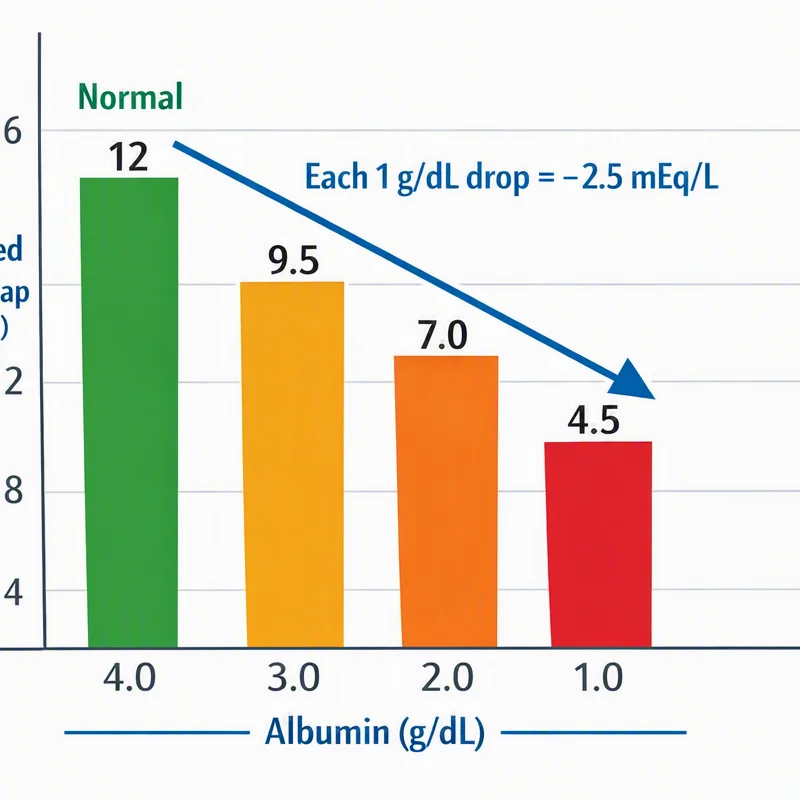
The anion gap is also influenced by albumin, the main negatively charged protein in the blood. When albumin is low, the gap may appear reduced than expected even if no major acid-base problem is present. This is one reason clinicians may adjust their thinking using a adjustment factor for albumin in certain situations.
Because albumin affects the measured gap, a apparently normal result on a blood panel does not always rule out a clinically important problem. Likewise, a slightly outside value does not automatically mean disease. The full clinical assessment depends on the rest of the patient’s picture, including the electrolyte levels, other tests, and symptoms.
In practice, the anion gap is most helpful when it is matched to the lab’s expected range and then evaluated for trends. A result that is near the upper end of normal may still matter if the patient has signs of acid buildup. That is why the anion gap remains a useful helpful indicator in routine medical assessment.
What’s a Elevated Anion Gap Suggest?
A raised anion gap usually indicates that acid compounds or additional negatively charged substances have collected in the blood. This pattern is often associated with acid-base imbalance. Put simply, the calculated bicarbonate decreases as it is used to buffer acids, while the gap increases because of increased undetected ions.
Both classic causes of high anion gap are elevated lactate and acid buildup from ketones. With lactic acidosis, the body builds up lactate, often because tissues are not getting enough oxygen or because of severe illness. When ketoacidosis develops, ketones rise, usually in settings such as diabetes, prolonged fasting, or severe carbohydrate deficiency.
A raised gap may also occur in additional kinds of systemic acidemia. The key idea is that the blood holds extra acids that are not directly measured in the standard electrolyte measurements. The anion gap becomes a useful clue that helps narrow the possible source.
For this reason, a high anion gap is not just a number; it is a sign that needs further evaluation. The next step is usually to review the rest of the labs, the patient’s symptoms, and the likely source of the acid load. That value is part of a broader clinical interpretation, not the final diagnosis.
What Is a Decreased Anion Gap Mean?
A decreased anion gap is rarer than a high one, but it can still be important. A leading cause is hypoalbuminemia, or low albumin. Since albumin normally contributes negative charge, a drop in albumin can lower the calculated gap.
Another possible explanation is multiple myeloma, a condition that can change the pattern of proteins in the blood and shift the measured balance of ions. In these cases, the low value may anion gap normal values children provide a clue that further evaluation is needed.
Sometimes a low value is not caused by disease at all. Lab error or a sample problem can produce an abnormal result that resolves when the test is repeated. Because of this, a very low number should be verified before drawing conclusions.
When the anion gap is low, clinicians usually look at the full blood chemistry panel and consider whether the patient has low albumin, a protein disorder, or a measurement issue. A low result may have clinical meaning, but it should always be interpreted carefully within the larger medical assessment.
Common Causes That Alter the Anion Gap
A number of conditions can move the anion gap higher or lower. Some are related to acid buildup, while others suggest altered proteins, kidney management of acids, or measurement problems.
- Kidney failure can reduce acid excretion and lead to a high anion gap. Kidney disease may gradually impair acid-base regulation and alter the electrolyte pattern. Renal failure is an additional common setting in which acids collect and the gap rises. Toxins can cause a high gap by bringing in unmeasured acids or disturbing metabolism. Salicylates are an major toxin category and can be involved in salicylate poisoning, which may distort acid-base status in different ways.
This matters because the anion gap is not just a mathematical result. It helps identify the type of problem behind an abnormal laboratory result. A high value may prompt a search for acids, toxins, or decreased clearance. A low value may prompt consideration of low protein states or analytical issues.
In many cases, the anion gap is one piece of a larger picture that includes symptoms, kidney function, and the rest of the serum electrolytes. That is why knowing the likely cause of an abnormal result is just as important as learning the formula itself.
Used well, the gap acts as a practical interpretive guide for clinicians and patients reviewing a screening test result. It can point toward hidden acid problems, help separate different forms of acidosis, and support more targeted testing when needed.
FAQs About the Anion Gap
How is calculated the anion gap from lab values?
Use the anion gap formula: sodium less the total of chloride and bicarbonate. In other words, anion gap = sodium - (chloride + bicarbonate). You can also enter the same numbers into an Anion Gap Calculator to get a fast calculation output. Make sure the values come from the same blood test or BMP so the result matches the correct serum electrolytes.
What would be the normal anion gap range?
The normal range changes by laboratory, testing method, and the lab’s normal interval. Many labs use a relatively narrow interval, but there is no single number that fits every setting. For the most accurate clinical interpretation, compare the result with the range listed on the report and consider whether albumin is normal.
Why does a high anion gap happen?
A increased anion gap usually happens when extra acids build up in the blood, leading to acid-base imbalance. Common examples include lactic acidosis and ketoacidosis. It can also occur with certain toxic substances or in renal failure, where the body cannot remove acids effectively. The gap helps identify hidden acids that are not directly measured in routine labs.
Is a low anion gap a sign of a problem?
Yes. A low anion gap can be seen with hypoalbuminemia, multiple myeloma, or a laboratory error. Sometimes it is not clinically important, but it should not be ignored if it is unexpected or persistent. Rechecking the test result and reviewing the rest of the blood panel can help determine whether the result is meaningful.
Is albumin correction needed when calculating the anion gap?
In many cases, yes, particularly when albumin is low. Because the albumin level affects the measured balance of charges, a low albumin level can make the anion gap look falsely low. In those cases, clinicians may use a adjustment factor to better estimate the true gap. This improves analysis and helps avoid missing a real acid-base issue.