What the Gap Measures
The anion gap is a useful way to evaluate electrolyte balance and help detect causes of acid buildup. It is not a direct measurement of a single component in blood chemistry. Instead, it is a calculated value that represents the difference between commonly measured positive and negative ions in the plasma.
An anion gap calculator helps medical users quickly estimate whether there may be extra additional anions present. These may appear in conditions that affect acid-base balance, especially when the blood shows a pattern consistent with acid-base disturbance.
In simple terms, the anion gap compares measured sodium against measured chloride and bicarbonate. Because those three values are usually included in an electrolyte panel, the calculation is simple to apply in routine care. The result can support clinical interpretation of an electrolyte imbalance, especially when a patient has reduced bicarbonate or other signs of acid retention.
Although the anion gap is often taught as a standalone concept, it is most useful when interpreted alongside other laboratory values, symptoms, and the larger pattern of the blood chemistry. A normal result does not always rule out disease, and an abnormal result does not stand alone as a diagnosis. It is a assessment tool that helps narrow the possibilities.
How to Operate an Anion Gap Calculator for Serum Sodium
A dependable anion gap calculator usually requests three numbers: serum sodium, serum chloride, and serum bicarbonate. These are usually reported as part of a routine metabolic panel or a similar chemistry panel. The calculator then does the same math a clinician would use manually.
The calculator is easy to use:
- Enter the serum sodium level. Input the serum chloride value. Input the serum bicarbonate value. Check the output and match it with the normal reference range.
Since serum sodium anchors the formula, the calculator shows the balance between major measured cations and anions. A change in sodium, chloride, or bicarbonate can change the result, which is why the calculator is valuable for acid base interpretation.
As an example, a patient with a normal sodium level but a reduced bicarbonate and increased chloride may still have a normal anion gap. Another patient with reduced bicarbonate and no compensatory chloride rise may have a high anion gap. The calculator makes clear that pattern rapidly.
When reviewing the result, consider whether the numbers fit the broader clinical picture. If the patient has vomiting, dehydration, diabetes, kidney disease, or suspected poisoning, the calculated gap becomes more informative. The same is true when comparing serial values over time, since shifting electrolytes can show whether a metabolic state is getting better or declining.
Anion Gap Formula & Detailed Determination
The usual anion gap formula reads:
Anion gap = sodium − (chloride + bicarbonate)
Some clinical laboratories use slight differences, but this version is the most familiar and is the most straightforward to follow for manual calculation. It uses the measured sodium, chloride, and bicarbonate values from the blood.
Below is a stepwise way to work out anion gap:
- Start with the measured sodium value. Combine the measured chloride and bicarbonate values. Subtract that total from sodium. The result is the anion gap.
For example:
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Working: 140 − (104 + 24) = 12
This value is usually inside the expected range. In this example, the blood chemistry suggests a balanced relationship among the major measured ions.
Why does this work? Because the body contains both measured ions and unmeasured anions. The formula estimates the difference between positively charged and negatively charged components in the plasma. If the number is higher than expected, it may reflect extra acids or other unmeasured substances. That is why the anion gap is valuable in evaluating metabolic acidosis and related conditions.
Some people prefer to think about the formula as a shortcut for identifying whether the acid-base system is balanced. If bicarbonate drops and chloride does not rise enough to offset it, the gap changes. If bicarbonate drops and chloride rises in parallel, the gap may remain normal even though there is still a major acid-base issue.
Normal Range and Interpreting Results
The normal anion gap is often reported within a tight normal reference range, but the exact interval depends on the laboratory method and the analyzer used. This is why it is important to interpret results using the reference range provided with the test instead of relying on a single universal number.
In general, a normal anion gap suggests that measured blood electrolytes are relatively even and that there is no obvious accumulation of many unmeasured acids. Still, normal results do not exclude every acid-base problem. A patient can still have acidosis, especially non-gap forms where chloride increases to keep the overall balance stable.
A increased anion gap suggests that extra acids or other unmeasured anions are present. This finding often points toward acidic metabolic imbalance and should prompt a closer look at causes such as lactate, ketones, kidney dysfunction, or toxins. The result is not a diagnosis by itself, but it is a valuable clue.
Albumin also matters because it is a major unmeasured negatively charged protein in plasma. When albumin is low, the measured gap may appear artificially normal. For this reason the raw number should be anion gap clinical significance interpreted alongside albumin concentration and the patient’s overall state.
In practice, the most useful approach is to interpret results in context:
- A normal gap with low bicarbonate may suggest a non-gap metabolic problem. Low bicarbonate with a high gap points toward a high-gap metabolic acidosis pattern. Decreased albumin can decrease the apparent gap and obscure a true abnormality.
Revised Anion Gap and Albumin Correction
Since albumin plays a major role in the anion gap, hypoalbuminemia may conceal a true elevation. In that situation, a corrected anion gap is more useful than the unadjusted value. The goal is to correct for albumin so the result more accurately reflects the patient’s actual acid-base state.
There are several albumin correction approaches, but the key idea is simple: lower albumin lowers the observed anion gap. If albumin is reduced, the clinician should apply an adjustment before concluding that the gap is normal.
One common correction method includes a set amount to the measured gap for each decrement in albumin below normal. The exact adjustment may vary by formula, so a calculator that includes albumin can be very useful. The important clinical principle is that hypoalbuminemia can hide a high anion gap.
Why this matters: a patient with low albumin and elevated lactate may have a corrected value that meaningfully alters interpretation. Without adjustment, the raw anion gap can downplay the severity of the metabolic derangement.
Review this clinical reasoning:
- The measured gap looks normal. Albumin is decreased. With albumin adjustment, the gap becomes elevated.
That shift can reveal hidden acidosis and guide further evaluation. In other words, the corrected anion gap is not just a mathematical exercise. It is a way to avoid missing clinically important acid-base abnormalities.
If you use an anion gap calculator, always check whether it includes albumin input or provides a separate albumin correction field. If not, you may need to revise the number manually when albumin is abnormal.
Typical Causes of an Abnormal Anion Gap
An abnormal result is usually a clue that something is changing the body’s acid load or electrolyte profile. The most common causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and toxins.
Lactic acidosis happens when lactate accumulates because tissues are not using oxygen effectively or because metabolism is stressed. This often appears in severe illness, shock, hypoperfusion, or other states of tissue hypoxia. The extra lactate acts as an unmeasured anion and raises the gap.
Ketoacidosis occurs when ketone bodies accumulate, commonly in diabetes but also in starvation or alcohol-related states. These ketones contribute to metabolic acidosis and raise the gap.
Renal failure can also lead to an elevated gap because impaired kidneys do not remove acids effectively. As acids accumulate, the plasma shows more unmeasured anions and less bicarbonate.
Toxins are another important category. Certain ingestions introduce acids or acid precursors that produce a high-gap pattern. In these cases, the anion gap may provide an early clue that directs urgent evaluation.
Frequent causes for a normal anion gap with acidosis include gastrointestinal bicarbonate loss or renal tubular causes. In those cases, chloride often rises to replace lost bicarbonate, which is why the gap can remain normal despite serious illness.
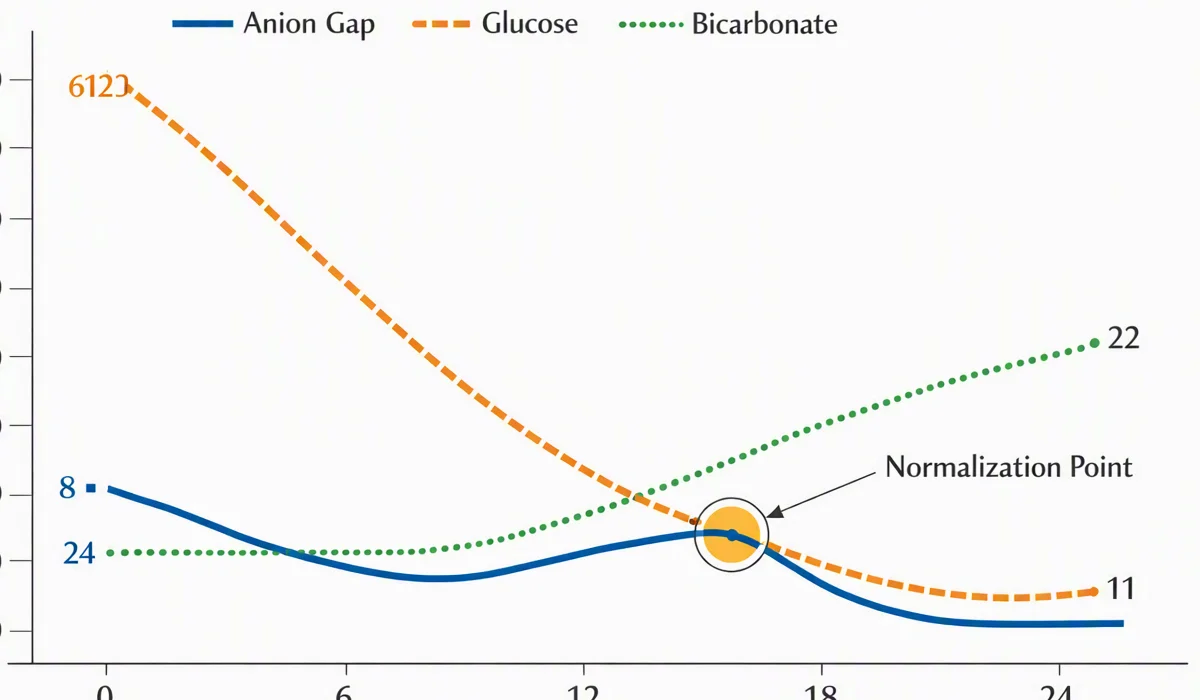
This pattern can be recognized can be summarized this way:
- High anion gap: consider extra acids or retained acid. Normal anion gap: think bicarbonate loss with compensatory chloride rise. Be sure to review sodium, chloride, bicarbonate, and the full clinical picture.
Clinical Context and Acid-Base Disorders
The anion gap is most useful when placed within the broader framework of acid-base imbalances. It is just one part of the picture. A patient may have a metabolic alkalosis, respiratory acidosis, or mixed condition in addition to an abnormal gap, and the overall pattern is more important than the value itself.
In alkalotic states, bicarbonate is raised rather than reduced, so the anion gap is not the main indicator. Still, the gap may help identify a mixed condition if a patient has both alkalosis and a hidden elevated-gap process.
In carbon dioxide retention, carbon dioxide retention is the main problem, not an isolated bicarbonate change from acid accumulation. However, long-standing lung disease can lead to secondary changes in bicarbonate that complicate interpretation. The anion gap can help confirm or exclude an accompanying metabolic disorder.
This is why a good acid base interpretation uses more than one number. A clinician may review pH, CO2, bicarbonate, sodium, chloride, and albumin together. The anion gap then becomes a useful clinical tool for identifying whether the disturbance is metabolic, respiratory, or mixed.
Another helpful concept is the delta gap. This compares the rise in anion gap with the fall in bicarbonate and can suggest whether more than one metabolic process is happening at once. It is especially useful when the clinical picture does not match the expected pattern. A delta gap can reveal a hidden metabolic alkalosis or an additional non-gap acidosis alongside a high-gap disorder.
In practical terms, the anion gap supports bedside reasoning:
- Is there acid-base acidosis? Is the gap increased or unchanged? Is albumin low enough to require compensation? Do the results match the symptoms and other laboratory values?
Frequently Asked Questions
What is the anion gap calculator with serum sodium used for?
This anion gap calculator with serum sodium is used to quickly estimate anion gap from routine blood chemistry values. It helps assess acid-base balance, detect possible metabolic acidosis, and identify patterns such as a high anion gap or normal anion gap. It is particularly useful when reviewing an electrolyte panel that includes sodium, chloride, and bicarbonate.
How do you calculate anion gap from sodium, chloride, and bicarbonate?
Apply the standard anion gap formula: sodium − (chloride + bicarbonate). Input the measured sodium, chloride, and bicarbonate values, then subtract the sum of chloride and bicarbonate from sodium. This yields the calculated gap, which can then be compared with the normal reference range.
What is a normal anion gap considered to be?
A normal anion gap is based on the laboratory’s method and reference anion gap end stage renal disease interval, so the best answer is the range printed with the test results. In many settings, the normal reference range is relatively narrow. Always interpret the result using the lab’s reported range and the patient’s overall clinical picture, especially if albumin is abnormal.
Why is the anion gap corrected for albumin?
You correct the anion gap for albumin because low albumin can make the measured gap look falsely normal. With hypoalbuminemia, a true elevation may be hidden. A corrected anion gap gives a more accurate estimate of the acid-base state by adjusting for the loss of this major unmeasured anion. For this reason many clinicians choose to correct for albumin when interpreting results.
What does a high anion gap typically mean?
A high anion gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. It often points to metabolic acidosis, but the result should always be interpreted with other laboratory values, symptoms, and the full acid-base pattern.