What Is Renal Tubular Acidosis?
Renal tubular acidosis is an acid-base disorder in which the kidney tubules do not manage acid or bicarbonate normally. Even when the kidneys filter blood, the tubules are tasked for helping acid-base balance by reabsorbing bicarbonate and excreting hydrogen ions. When that process is disrupted, acid retention can develop and the result is a form of metabolic acidosis.
The key issue is not usually a failure of overall kidney filtration, but a problem in the kidney tubules themselves. This means a person can have renal tubular acidosis while other aspects of kidney function still look relatively preserved. Because bicarbonate is central to buffering acid, losses or impaired handling of bicarbonate quickly affect serum electrolytes and blood chemistry.
In practice, clinicians assess the pattern of sodium, chloride, bicarbonate, and potassium to understand whether the acid-base problem fits renal tubular acidosis. The lab picture often offers a strong diagnostic clue before more specialized testing is done.
How the Anion Gap Works
The anion gap is a computed value that helps assess serum electrolytes and recognize the form of acidosis present. It is commonly derived from sodium, chloride, and bicarbonate on a chemistry panel. A common version is:
Anion gap = sodium - (chloride + bicarbonate)
This calculation reflects electroneutrality, meaning the body’s positive and negative charges must remain balanced. If measured anions like chloride increase or bicarbonate decreases, the serum anion gap may remain normal or vary depending on what other acids are present. That is why an Anion Gap Calculator can be helpful during clinical interpretation.
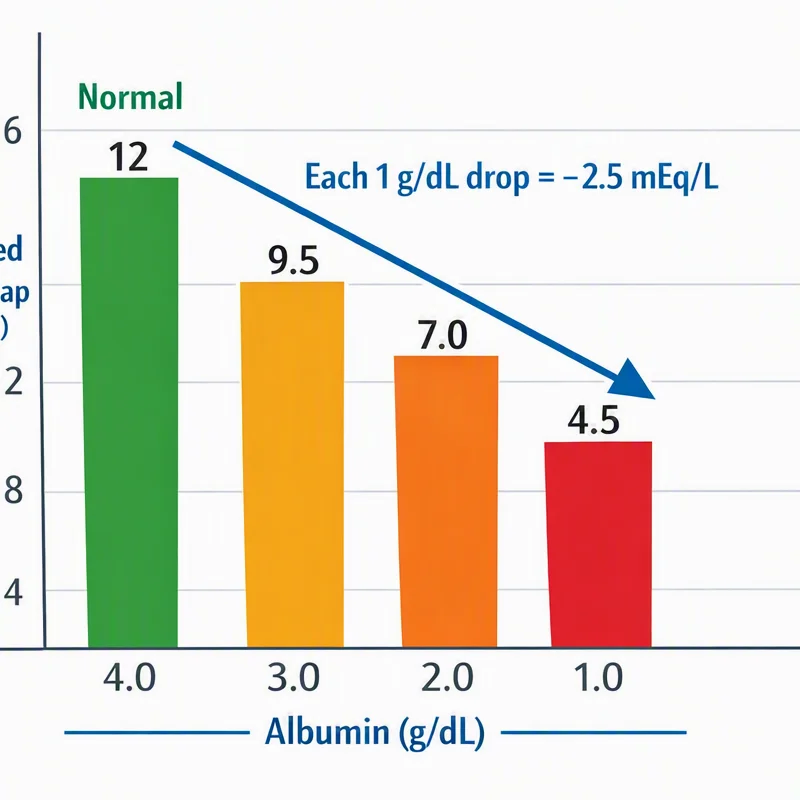
Because albumin is one of the primary unmeasured anions in blood, low albumin can make the measured anion gap seem lower than it truly is. In that situation, albumin correction or corrected anion gap calculation offers a more precise clinical assessment.
Does Renal Tubular Acidosis Increase or Normal the Anion Gap?
The majority of renal tubular acidosis produce a normal anion gap metabolic acidosis, sometimes referred to as hyperchloremic acidosis. The phrase “normal anion gap” means the gap is not elevated even though metabolic acidosis is present. This happens because bicarbonate is lost or not regenerated, and chloride rises to preserve electroneutrality.
So the usual answer is: renal tubular acidosis generally does not https://anion-gap-guide731.swiftnestly.com/posts/can-ethylene-glycol-cause-a-high-anion-gap cause high anion gap metabolic acidosis. Instead of that, it leads to a typical anion gap metabolic acidosis with hyperchloremia. That chloride rise is part of the body’s adaptive response to falling bicarbonate.
A elevated anion gap metabolic acidosis points to a different process. Lactic acidosis, ketoacidosis, uremia, and toxic ingestions are much more likely to raise the gap because they introduce additional unmeasured acids. In other words, if the Anion Gap Calculator shows a clearly elevated result, renal tubular acidosis may not be the whole explanation.
Types of Renal Tubular Acidosis and Its Lab Profiles
Distinct forms of renal tubular acidosis have varying mechanisms, but they share the same broad acid-base pattern: metabolic acidosis with a normal anion gap in most cases. Understanding the subtype matters because potassium, urine pH, and bicarbonate behavior assist in helping distinguish them.
Distal renal tubular acidosis develops when the distal nephron cannot properly acidify urine. This leads to impaired renal acidification, an elevated urine pH, and reduced ability to excrete acid. Serum bicarbonate falls, chloride rises, and potassium is often low.
Proximal renal tubular acidosis stems from impaired bicarbonate reabsorption in the proximal tubule. Initially in the process, bicarbonate loss is prominent. As the body adapts to the lower bicarbonate level, the acidosis often settles into a normal anion gap metabolic acidosis pattern. Potassium may also be low because of ongoing electrolyte imbalance.
Type 4 renal tubular acidosis is different from the other forms because it is commonly associated with low aldosterone effect and impaired potassium excretion. Potassium is often high rather than low, and the acidosis is still usually normal anion gap. This type is especially important in nephrology because it may appear in patients with diabetes, kidney disease, or medication-related changes.
In all subtypes, potassium is a major clue. Distal renal tubular acidosis and proximal renal tubular acidosis commonly produce hypokalemia, while type 4 renal tubular acidosis tends to produce hyperkalemia. That distinction can sharpen the differential diagnosis during clinical assessment.
How Chloride Often Rises in Renal Tubular Acidosis
Chloride frequently increases in renal tubular acidosis because the body works to maintain electrical balance when bicarbonate decreases. When bicarbonate is reduced, chloride retention helps maintain electroneutrality. This is the reason the disorder is commonly labeled hyperchloremic acidosis.
The increase in chloride is not the primary disease itself; it is one of the compensatory mechanisms that follow bicarbonate loss. The blood chemistry changes because the drop in serum bicarbonate must be offset by another measured anion. Chloride takes that role in many cases, especially in normal anion gap metabolic acidosis.
This pattern is useful in laboratory interpretation. If a patient has metabolic acidosis, low bicarbonate, and elevated chloride with a normal anion gap, renal tubular acidosis becomes a stronger diagnostic clue. The result points toward an acid-base disorder driven by renal acidification problems rather than by accumulation of unmeasured acids.
When a Elevated Anion Gap Suggests A Different Process
A elevated anion gap metabolic acidosis usually means another process is causing acid buildup. The most common causes include lactic acidosis, ketoacidosis, and uremia. Toxic ingestions can also create a high gap by introducing unmeasured acids or acid precursors to the blood.
This distinction matters because renal tubular acidosis and high anion gap disorders can both present with low bicarbonate and acid-base symptoms, but their causes are different. In lactic acidosis, tissue hypoperfusion or impaired oxygen delivery leads to lactate accumulation. In ketoacidosis, ketone bodies accumulate from insulin deficiency or starvation. In uremia, retained acids from kidney failure increase the serum anion gap. Toxic ingestions may add substances that directly alter blood chemistry.
So if the Anion Gap Calculator shows a high result, do not assume renal tubular acidosis. A careful differential diagnosis is needed, especially if the electrolyte panel also suggests dehydration, shock, diabetes, or advanced kidney disease.
How to Work with an Anion Gap Calculator in Clinical Assessment
An Anion Gap Calculator is most useful when it is combined with the rest of the electrolyte panel. The calculator can quickly show whether the serum anion gap is within normal limits, high, or potentially affected by low albumin. That makes it an useful tool for laboratory interpretation rather than a isolated diagnosis.
First, examine sodium, chloride, and bicarbonate from the electrolyte panel. Then work out the anion gap and assess whether the result fits a normal anion gap metabolic acidosis or a high anion gap metabolic acidosis. If albumin is low, apply albumin correction or use a corrected anion gap so the number is not misleadingly normal.

Here is the typical sequence:
- Review the blood chemistry for sodium, chloride, and bicarbonate. Determine the serum anion gap with an Anion Gap Calculator. Examine albumin and use albumin correction if needed. Compare the result with the clinical picture and acid-base disorder suspected. Look for clues of renal tubular acidosis, lactic acidosis, ketoacidosis, or uremia.
This approach assists distinguish an acid-base pattern caused by bicarbonate loss from one caused by added acids. It also improves clinical assessment when the diagnosis is not obvious from symptoms alone.
Typical Symptoms and Reasons That Point to RTA
Symptoms of renal tubular acidosis can be hard to notice, especially early on. Some people are identified because of unusual blood chemistry rather than symptoms. Other people develop weakness, fatigue, electrolyte imbalance, or signs related to chronic acid retention.
Common causes include kidney disease, autoimmune disease, and medications that interfere with tubular function. Dehydration can also worsen the picture by raising serum electrolytes and taxing renal acidification. In many patients, the cause is recognized only after a careful nephrology evaluation.
When assessing causes, it helps to link the lab pattern with the history. Autoimmune disease may point toward distal renal tubular acidosis. Certain medications may contribute to proximal renal tubular acidosis or type 4 renal tubular acidosis. Kidney disease itself can make harder interpretation because it may overlap with other forms of metabolic acidosis.
Urine pH can also support the diagnosis. In distal renal tubular acidosis, the urine pH may remain inappropriately high despite systemic acidosis. That clue, combined with bicarbonate loss or potassium abnormalities, reinforces the suspicion of a tubular problem rather than another acid-base disorder.
Frequently Asked Questions About RTA and Anion Gap
What is the standard anion gap in renal tubular acidosis?
The usual anion gap in renal tubular acidosis is normal. Most cases produce non-anion gap metabolic acidosis, also called hyperchloremic acidosis, because bicarbonate falls while chloride rises to maintain electroneutrality. A normal anion gap does not mean the acidosis is mild; it only describes the pattern of serum electrolytes.
Why does renal tubular acidosis usually cause a normal anion gap?
Renal tubular acidosis usually causes a normal anion gap because the main problem is bicarbonate loss or impaired acid secretion, not accumulation of unmeasured acids. As bicarbonate drops, chloride commonly increases to preserve balance. That produces a metabolic acidosis pattern without a high serum anion gap.
Could RTA ever lead to a high anion gap?
By itself, renal tubular acidosis usually doesn't cause a increased anion gap. When a increased anion gap is found, evaluate for another acid-base problem such as lactic acidosis, diabetic ketoacidosis, uremia, or toxic ingestions. At times more than one process is going on at the same time, so the calculator result should be considered in the full clinical context.
In what way does albumin change an anion gap calculation?
Albumin is a major unmeasured anion, so low albumin can lower the measured anion gap and make it seem normal even when an acid problem is present. For this reason albumin correction is important. A corrected anion gap gives a more precise view of the real serum anion gap, especially during laboratory interpretation of metabolic acidosis.
What lab tests can help confirm renal tubular acidosis?
Useful tests include an electrolyte panel, serum bicarbonate, potassium, chloride, albumin, and a calculated or corrected anion gap. Urine pH is also important because it helps assess renal acidification. Depending on the suspected subtype, nephrology may order additional urine studies or other medical testing to confirm the diagnosis and separate it from other acid-base disorders.