What the anion gap Reflects in Pediatrics
The anion gap is a practical way to examine the connection between key electrolytes in the blood and to better understand acid-base balance. In children, it is often applied as part of a larger review of serum chemistry and lab results when a clinician is trying to understand whether there may be an electrolyte imbalance or an acid-base disorder.
Although the anion gap is not a direct test of a specific acid, it can serve as a helpful clue. It helps clinicians infer whether extra unmeasured acids may be present in the blood. This makes it especially useful in pediatrics, where symptoms such as vomiting, poor intake, breathing changes, or lethargy may be connected to a broader metabolic disturbance.
The concept is simple: the body’s major positively charged and negatively charged particles should stay in a balanced relationship. The routinely measured values used in this estimate are sodium, chloride, and bicarbonate. Because these are part of routine serum electrolytes, the anion gap can often be assessed from a standard blood test without any extra special collection.
In pediatrics, interpretation always depends on the patient context. A single anion gap value does not establish illness by itself. Instead, it provides supportive context for the full assessment, including symptoms, hydration status, and other laboratory data.
How an Anion Gap Calculator Works
An Anion Gap Calculator applies a fundamental calculation formula based on common blood chemistry anion gap clinical significance values. In the commonly used form, the calculator subtracts the measured chloride and bicarbonate from the sodium level:
Anion gap = sodium − (chloride + bicarbonate)
This straightforward formula gives an anion gap value that can be evaluated with a reference interval or normal range. The calculation itself is simple, but the clinical interpretation is where pediatric context matters most.
Because the formula uses a sodium level, chloride level, and bicarbonate level, any issue influencing those numbers can change the result. For example, dehydration, fluid shifts, or changes in acid production can alter the pattern seen on a chemistry panel. An unexpected result may reflect actual physiology, but it can also reflect a lab measurement problem or another transient factor.
Many calculators are designed to calculate the gap quickly from an electrolyte panel, but they do not replace judgment. A calculator can be a screening aid, not a diagnosis. In children, that distinction matters because age, growth, and illness can shape the meaning of the result.
Some tools also allow a correction for albumin, since albumin contributes to the gap and can affect interpretation when it is low. That added step can be helpful when trying to understand whether a result truly reflects an acid-base disturbance or whether low protein levels are changing the reading.
Childhood Reference Values and What Varies With Age
The expected anion gap in children is not necessarily identical to the adult reference range used by every laboratory. A pediatric reference range may vary depending on the testing technique, the analyzer, and the local laboratory’s criteria. This is why a single number should never be read in isolation.
In real-world practice, the most important question is whether the value is within the lab’s stated normal interval. Even within pediatrics, the interval may change a little with age, growth, and body composition. Younger children may have altered expected chemistry patterns than older children, and newborns have their own separate factors. For this reason, the same anion gap measurement can have varying significance depending on the pediatric patient.
When assessing a chemistry panel, clinicians look at the full picture: the anion gap, bicarbonate, chloride, sodium, and often albumin. A value that is only mildly beyond the expected interval may be less concerning than one that is clearly abnormal and paired with indications of illness. The result is best understood as part of overall clinical assessment, not as a standalone diagnosis.
It is also important to remember that a “normal” result does not always rule out a problem. Some children with a real metabolic disturbance may still have a gap that appears normal if the underlying condition is early, mild, or influenced by other circumstances. Likewise, a borderline value may be less meaningful if the child is otherwise well.
Interpreting a Raised Anion Gap in a Child
A raised anion gap often suggests that excess acids are accumulating in the body. In a child, this can indicate metabolic acidosis, which is a condition where the blood becomes less alkaline than expected. The anion gap does not show the exact cause, but it helps reduce the list of possibilities.
One typical cause is the accumulation of ketones, which can happen when the body is burning fat for energy instead of using glucose as usual. This pattern is especially significant in diabetic ketoacidosis, a medical emergency that can occur in children with diabetes. In that situation, the high anion gap may be one of the first laboratory clues that something serious is going on.
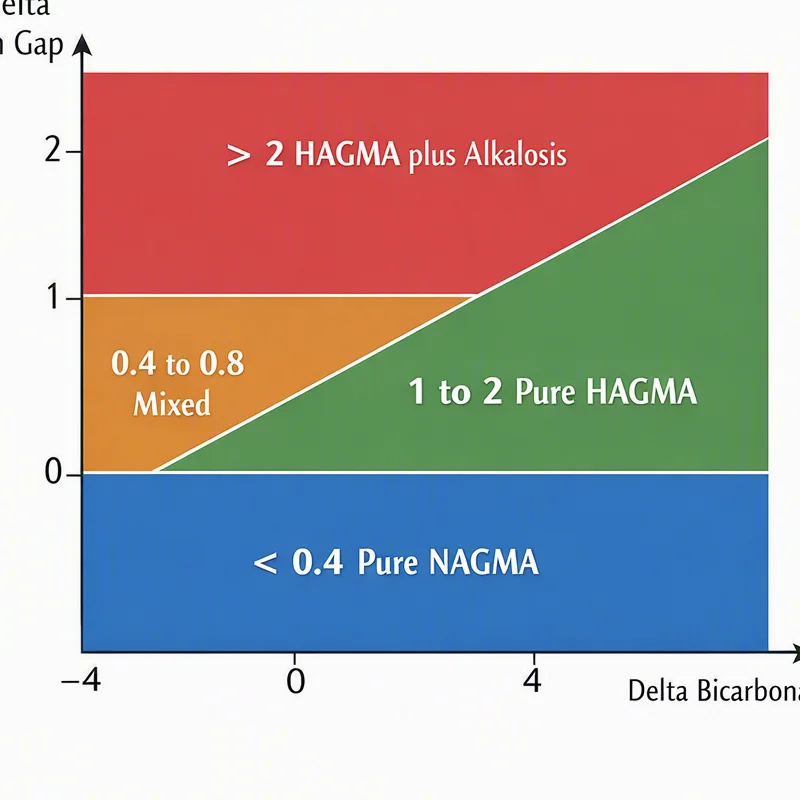
Other situations can also raise the gap. Severe illness, poor intake, or abnormal tissue metabolism may cause an acid load that the body cannot easily clear. In pediatrics, a high value should always be reviewed alongside symptoms such as rapid breathing, vomiting, abdominal pain, confusion, or unusual fatigue.
The value is best understood as a signal rather than a final answer. A child with a high anion gap may need repeat labs, blood glucose testing, or a fuller assessment of acid-base status. The result offers a diagnostic clue, but the cause must be identified through follow-up evaluation.
How to Understand a Reduced Anion Gap in a Child
A reduced anion gap is rarer than a higher value, but it can still be relevant. One major reason is a change in albumin, the main protein in the blood that helps support the usual distribution of charged particles. If albumin is low, the gap may look lower than expected even when the child is not acutely ill.
A low value can also occur because of laboratory error or another technical issue affecting the chemistry panel. For that reason, a unexpected result should be examined closely before making conclusions. Repeating the test may be reasonable if the number does not fit the child’s condition or if the sample quality is uncertain.
More rarely, a low anion gap may point to other metabolic or measurement issues. However, in daily pediatric practice, the first steps are usually to verify the result and review albumin, total protein, anion gap renal failure and the rest of the serum chemistry panel. The main goal is to decide whether the value represents a true physiologic change or an unexpected result caused by testing conditions.
Because a low anion gap is often subtle, it should not be ignored if it persists. Even so, it is usually interpreted in the context of the complete medical picture, not as an isolated diagnosis.
Typical Causes of Atypical Anion Gap Results
A number of conditions can alter the anion gap in children. The result pattern matters because it can point toward various underlying mechanisms affecting serum electrolytes and acid-base balance.
- Dehydration can increase blood values and affect how the chemistry panel appears, especially if the child has been losing fluid from throwing up, loose stools, or poor intake. Kidney disease can limit the body’s ability to manage acids and electrolytes, which may lead to a high anion gap or other abnormalities on lab results. Diabetic ketoacidosis is a major cause of high anion gap metabolic acidosis in children and should be treated as an urgent condition. Toxic ingestion of certain substances can affect metabolism or acid handling and may produce a significant acid-base disorder.
These conditions do not all present the same way. Certain cases lead to obvious symptoms, while others are first noticed on a blood test ordered for another reason. This is why the anion gap is useful as a screening tool: it may reveal a clue before the full story is clear.
Still, the result is only part of the picture. A child with dehydration may improve quickly with appropriate care, while a child with kidney disease or toxic ingestion may need urgent evaluation. The number alone cannot separate these possibilities.
Using the Result Safely
An Anion Gap Calculator can be a practical way to gauge whether a child’s lab values point to a standard pattern or suspected acid-base issue. But safe use means understanding its limits. The calculator should be paired with the full electrolyte panel, the child’s symptoms, and guidance from a pediatrician or other qualified clinician.
Before drawing conclusions, verify that the blood test values are current and from a reliable source. Small changes in the sodium, chloride, or bicarbonate levels can alter the calculation. If the child is sick, the numbers may change over time, which is why repeat lab results are sometimes necessary.
If the result is abnormal, the next step is usually not to self-diagnose. Instead, it may lead to a focused medical review, which can include checking blood glucose, ketones, kidney function, hydration status, and sometimes a more detailed acid-base assessment. This is especially important when the child has symptoms such as confusion, fast breathing, severe vomiting, or reduced alertness.
Parents and caregivers should think of the calculator as a screening aid that helps organize information. It can support questions like, “Does this chemistry panel fit with a metabolic problem?” or “Is there a reason to ask for a follow-up evaluation?” That approach is much safer than using the number by itself to make decisions.
If a child has concerning symptoms, the best action is to contact a clinician promptly. A calculator can help interpret context, but it cannot replace medical judgment, physical examination, or a full review of the blood test.
Frequently Asked Questions About Anion Gap in Children
Why is an anion gap calculator used in children?
An anion gap calculator is used to calculate the anion gap from standard blood chemistry values such as sodium, chloride, and bicarbonate. In children, it helps screen for possible electrolyte imbalance or acid-base disorder and may provide a useful diagnostic clue when reviewing lab results. It does not diagnose a specific illness on its own.
What is a normal anion gap range for children?
The normal range depends on the laboratory’s pediatric reference range and the method employed. Children may have mildly different reference values than adults, so the lab’s stated interval should always guide interpretation. A result should be reviewed in context with the full serum chemistry panel and the child’s symptoms.
What causes a high anion gap in a child?
A high anion gap can occur when extra acids accumulate in the body, leading to metabolic acidosis. Common causes include diabetic ketoacidosis, kidney disease, serious illness, and some forms of toxic ingestion. Ketones are an especially important clue when the body is using fat for energy instead of glucose.
Can a low anion gap be serious in children?
A low anion gap is often not as urgent than a high one, but it can still matter. It may be related to low albumin, a testing issue, or less commonly another medical problem. Because laboratory error can also cause an unexpected result, repeat testing or follow-up review may be needed if the number does not fit the clinical picture.
Should parents rely on an anion gap calculator without a doctor?
No. Anion Gap Calculator should not replace a pediatrician or other clinician. It can help estimate a value from a blood test, but interpretation requires supportive context, including the child’s symptoms, other lab values, and the broader clinical situation. It is a screening tool, not a diagnosis.