What the Anion Gap Measures
The anion gap is a derived value that enables clinicians understand acid-base balance and spot unmeasured anions in the blood. It is most often derived from a basic electrolyte panel using serum sodium, serum chloride, and serum bicarbonate. In practical terms, the anion gap is a tool for laboratory interpretation that can point toward metabolic acidosis even before the full cause is known.
The calculation reflects the difference between the main measured cations and anions in serum. Because the body contains many charged particles that are not directly measured, the anion gap calculation can expose hidden acids from acid accumulation, toxins, or organ dysfunction. A higher-than-expected value often suggests a pathologic process such as high anion gap metabolic acidosis, while a normal value may lead clinicians to consider other causes of illness.
An anion gap calculator simplifies this step and reduces the chance of arithmetic mistakes during clinical assessment. In a toxicology setting, that efficiency matters because the result may trigger toxicology screening, more urgent lab testing, or immediate treatment. Although the number itself is simple, its interpretation can be highly consequential.
Reasons Why Toxic Ingestion Can Raise the Anion Gap
Poisoning is a major cause of raised anion gap because many poisons create acids directly or disrupt metabolism in ways that raise acid production. In these cases, the body accumulates unmeasured anions that raise the calculated gap. This pattern is key to identifying high anion gap metabolic acidosis in a poisoning workup.
Some exposures, especially toxic alcohols, are well-known causes. Methanol and ethylene glycol are metabolized into acidic compounds that drive metabolic acidosis. Soon after ingestion, the osmolar gap may be elevated before the anion gap rises, while later the anion gap can become markedly abnormal as toxic metabolites accumulate. This timing issue is one reason why both values are useful in clinical assessment.
Other poisonings can raise the gap through lactic acidosis, impaired tissue oxygen delivery, seizures, shock, or mitochondrial dysfunction. Salicylate toxicity can also produce complex changes in acid-base balance, sometimes combining respiratory alkalosis with metabolic acidosis. The underlying process may involve increased lactate, impaired clearance, or the addition of other acids into circulation.
In many cases, the anion gap is not the diagnosis itself but a diagnostic signal. It helps clinicians recognize that something is driving acid-base abnormality and may warrant immediate toxicology evaluation. This makes it especially useful when symptoms are nonspecific, such as nausea, altered mental status, tachypnea, or unexplained systemic toxicity.
How to Use an Anion Gap Calculator
An anion gap calculator generally requires only the values from an electrolyte panel: serum sodium, serum chloride, and serum bicarbonate. The common formula is sodium minus the chloride value and bicarbonate. The resulting figure estimates the difference between measured cations and anions and assists in screening for hidden acid load.
For toxic ingestion, calculator use should go beyond the raw number. A careful review of albumin is important because low albumin lowers the measured gap and can hide clinically meaningful abnormalities. This is why many clinicians calculate a corrected anion gap. Albumin correction enhances sensitivity when evaluating possible poisoning, especially in hospitalized or critically ill patients with hypoalbuminemia.
Using the calculator in sequence can aid timely decision-making:
- Confirm the electrolyte panel values are current and internally consistent. Determine the raw anion gap. Assess albumin and determine the corrected anion gap if needed. Compare the result with the expected diagnostic threshold for concern. Read the result alongside symptoms, history, and other studies.
This process improves laboratory interpretation and helps align the gap with the broader clinical picture. For example, a patient with suspected ingestion may have an only mildly elevated raw gap but a clearly abnormal corrected value. That distinction can raise the level of concern for toxic ingestion and guide next steps in urgent management.
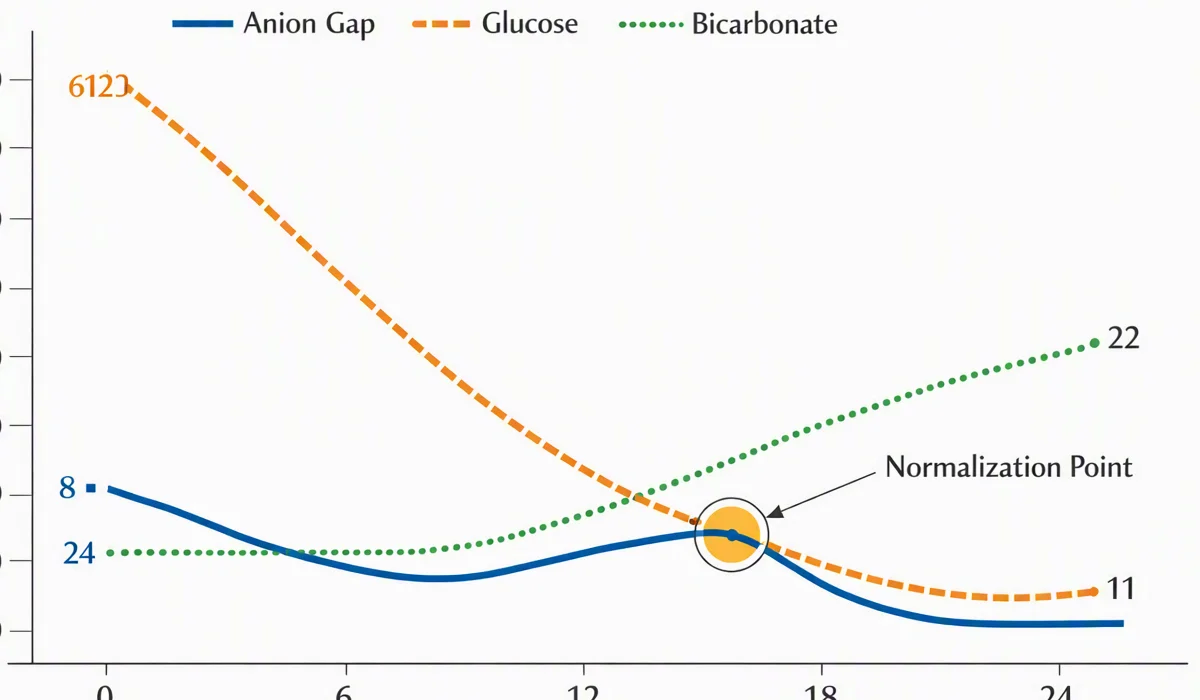
Common Poison-related Triggers of Elevated Anion Gap
Several toxic ingestions are frequently associated with increased anion gap and elevated anion gap metabolic acidosis. The most important include methanol, ethylene glycol, salicylates, and conditions with high levels of ketones. Each produces a slightly different pattern, but all can be associated with acid base derangements significant enough to require prompt recognition.
Methanol is metabolized into formic acid, which results to severe acidosis and can also cause visual symptoms. Ethylene glycol is converted to glycolic and oxalic acids, which may damage the kidneys and contribute to renal failure. The detection of crystals, worsening creatinine, or neurologic changes can reinforce suspicion, but the anion gap often provides the earliest laboratory clue.
Salicylates can cause a mixed pattern with early respiratory alkalosis and later metabolic acidosis. The acid-base picture may be hard to interpret unless the clinician considers toxicology. Ketones are another major source of elevated gap, especially in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation-related states. In these situations, ketoacidosis and the buildup of ketone bodies contribute to the abnormality.
It is also important to remember that toxins may act indirectly. Some exposures cause vomiting, hypoperfusion, seizure activity, or hypoxia, which can drive lactic acidosis. Others impair metabolism and increase acid production without obvious early symptoms. A calculated gap can therefore be a helpful bridge between nonspecific symptoms and a targeted toxicology diagnosis.
How to Read Values in Diagnostic Context
The anion gap should never be interpreted by itself. A increased result points to metabolic acidosis, but the next step is to assess whether the pattern matches a specific acid-base disorder. In toxic ingestion, the most important supporting studies often include the osmolar gap, an arterial blood gas, and a repeat electrolyte panel to confirm trends.
The osmolar gap can be especially helpful early in suspected exposure to toxic alcohols. A increased osmolar gap suggests unmeasured osmotically active substances, while a rising anion gap indicates accumulation of acidic metabolites. Together, these findings increase the suspicion for methanol or ethylene glycol poisoning.
An arterial blood gas offers direct information about pH, bicarbonate, and respiratory compensation. It helps identify whether there is severe acidemia, whether ventilation is compensating appropriately, and whether a mixed disorder is present. In a patient with poisoning, that data can influence airway, ventilation, and antidotal decisions.
Context matters just as much as numbers. Tachypnea, visual complaints, altered mentation, abdominal pain, renal injury, or hemodynamic instability all increase concern for systemic toxicity. When the lab pattern matches and the history is uncertain, the combination of anion gap, osmolar gap, and blood gas findings can support immediate toxicology consultation and treatment.
Limitations and Challenges of Anion Gap Calculation
While helpful, the anion gap has significant limitations. Among the most frequent is hypoalbuminemia. Because albumin is a major unmeasured anion, low levels can make a truly abnormal gap appear normal. This is why a corrected anion gap is so valuable in severely ill or deconditioned patients.
Another issue is mixed acid-base disorders. A patient may have both a high anion gap metabolic acidosis and a concurrent metabolic alkalosis or respiratory disturbance, which can mask severity. This is where the delta gap becomes important. The delta gap compares the change in the anion gap to the change in bicarbonate and can reveal hidden alkalosis or additional acid-base processes.
Lab error is another concern. Hemolysis, specimen issues, transcription problems, or delays in processing can distort the values used in the calculation. If the result does not match the clinical picture, repeating the test may be necessary before making major decisions. That caution is especially relevant when a poisoning workup is already underway.
Lastly, a normal anion gap does not fully exclude toxic exposure. Some ingestions are early in their course, some are partially treated, and some produce mixed patterns. For that reason, clinicians should treat the calculator as a decision support tool rather than a standalone rule-out test. The best practice is to combine laboratory interpretation with symptoms, exposure history, and serial reassessment.
When an Elevated Anion Gap Calls for Immediate Action
An high anion gap in the setting of suspected poisoning may represent a time-sensitive emergency. If there is altered mental status, severe acidemia, visual symptoms, kidney injury, or hemodynamic instability, the patient needs emergency evaluation immediately. Rapid communication with the poison center can help verify likely exposures and inform antidotal or supportive treatment.
Immediate action becomes even more important when toxic alcohols are suspected because delays can worsen outcomes. In certain situations, hemodialysis may be indicated to remove the toxin and correct severe acidosis. This is especially relevant for methanol and ethylene glycol poisoning, as well as for profound metabolic derangement that is not responding to initial measures.
Clinicians should also think beyond the number itself. A Find more information patient with a steadily climbing gap, worsening pH, or supportive osmolar gap findings may need urgent treatment even before confirmatory levels return. Early antidotal therapy, aggressive supportive care, and frequent reassessment are often central to urgent management.
If there is any uncertainty, the safest course is to step up care. Severe high anion gap metabolic acidosis can deteriorate fast, and a delayed response may allow more toxin metabolization and tissue injury. In practice, anion gap calculator is most valuable when it helps identify the point at which observation is no longer enough and urgent intervention is needed.
FAQ
What is considered a normal anion gap?
The anion gap reference range depends on the laboratory testing method, but a typical anion gap within normal limits is often roughly the low to mid teens. Because multiple analyzers and reference intervals vary, the local lab range should be used if possible. In toxicology, even a slight increase can matter if symptoms or exposure history suggest poisoning.
What effect does toxic ingestion have on the anion gap?
Toxic ingestion can increase the anion gap by adding acids to the blood, increasing acid retention, or altering metabolism so that acids such as lactate and ketone bodies accumulate. This causes increased anion gap metabolic acidosis. Exposures like methanol, ethylene glycol, and salicylates are important cases.
Which toxic alcohols produce a high anion gap?
The primary toxic alcohols associated with a raised anion gap are methanol and ethylene glycol. They produce acidic metabolites that lead to metabolic acidosis. A increased osmolar gap may be seen early, followed by a rising anion gap as the metabolism progresses.
Why must albumin be used to correct the anion gap?
Albumin is a major unmeasured anion, so reduced levels can reduce the observed gap and mask clinically significant disease. Calculating a adjusted anion gap enhances interpretation in patients with hypoalbuminemia. This is particularly helpful in critical illness, where the raw number may downplay the severity of a toxicologic problem.
When should a patient with an elevated anion gap seek urgent care?
Immediate medical care is important when an elevated anion gap occurs with symptoms of poisoning, disorientation, rapid breathing, severe vomiting, changes in vision, kidney impairment, or worsening illness. Since these can signal dangerous systemic toxicity, the patient should receive emergency evaluation. When a toxic exposure is possible, contacting a poison center right away is recommended, and hemodialysis may be needed in critical cases.