What the Anion Gap Indicates
The anion gap is a practical way to measure the balance between measured cations and measured anions in the blood. It is commonly applied as part of a serum chemistry or an electrolyte panel to help identify an electrolyte imbalance and guide clinical interpretation of acid-base disorders. In simple terms, the calculation compares serum sodium against serum chloride and bicarbonate to determine whether unmeasured acids may be present.
An anion gap calculator is a useful diagnostic tool because it helps translate raw laboratory values into an actionable calculated value. That value can indicate a hidden metabolic derangement, especially when a patient is in an acidotic state. The result does not stand alone; instead, it supports an interpretation framework that includes symptoms, laboratory context, and blood gas findings.
The core idea behind the anion gap is that plasma must remain electrically neutral. If sodium is higher than what chloride and bicarbonate account for, the remaining difference represents unmeasured ions such as lactate, ketones, or retained acids. This is why the anion gap is so important for recognizing hidden acidosis and other disturbances that may not be obvious from pH alone.
How to Use an Anion Gap Calculator
An anion gap calculator generally asks for the patient’s serum sodium, serum chloride, bicarbonate, and sometimes serum albumin. Several tools can also incorporate albumin correction to yield a more accurate corrected anion gap. Because albumin is a important unmeasured anion, low albumin can cause the gap appear deceptively normal.
The standard calculation formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Using this formula, the calculator gives a calculated value that can be compared with the normal reference interval. If the value is elevated, that indicates anion gap elevation and may indicate high-gap metabolic processes. If the value is normal but acidosis is present, a different pattern may be present, such as hyperchloremic acidosis.
When using the calculator, input the same chemistry values used in the lab report. If serum albumin is available, apply albumin correction so the result shows the true acid-base picture. This matters especially in critically ill patients, where low albumin can mask a significant acid load.
A helpful practical approach is to check the anion gap after checking the serum chemistry, then compare it with blood gas results. This gives a more complete clinical interpretation than either test alone. In other words, the calculator is especially helpful when it is part of a broader bedside assessment rather than a standalone number.
Analysis of Blood Gases and Acid-Base Assessment
Blood gas interpretation provides important insight to the anion gap by indicating the patient’s pH, partial pressure of carbon dioxide, and bicarbonate level. An arterial blood gas is often used to assess oxygenation and ventilation as well as acid-base status, while a venous blood gas can still be informative for pH and carbon dioxide trends in many clinical settings. These tests can aid interpretation, but they should be read with awareness of their distinct features.
The pH indicates whether the patient is acidemic or alkalemic. The carbon dioxide partial pressure helps determine whether the primary process is respiratory or metabolic, and bicarbonate indicates the metabolic component. If the pH is low and bicarbonate is low, the pattern often points toward metabolic acidosis. If carbon dioxide is also low, that may indicate respiratory compensation as the body attempts to counteract the acid load.
Blood gas analysis becomes especially useful when paired with the anion gap. A low pH with low bicarbonate and elevated anion gap strongly points to a high-gap acid load. A low pH with low bicarbonate but normal anion gap may instead suggest bicarbonate loss. This combination of findings supports a more precise acid-base diagnosis and avoids overreliance on a single calculated number.
It is also essential to consider whether the blood gas is showing a primary metabolic problem, a primary respiratory problem, or a mixed disorder. The pH provides the overall direction, while the partial pressure of carbon dioxide helps determine whether the lungs are compensating appropriately. That relationship is fundamental to meaningful clinical interpretation.
Equations, Expected Values, and Adjustments
The usual anion gap formula is easy to apply, but the clinical reading is more nuanced. Most labs use sodium minus chloride and bicarbonate, though some incorporate potassium. Because potassium is usually a small contributor, many clinicians choose the simpler version. What matters most is consistency and knowing which reference interval applies to the lab method being used.
The reference range for the anion gap changes by laboratory analyzer and local reporting standards. A usual normal anion gap is often in the low to mid teens, but the exact range depends on the assay and whether potassium is included. That is why the number should always be interpreted in the context of the lab’s own reference interval rather than an assumed universal cutoff.
Albumin correction is crucial when serum albumin is low. Because albumin is a major unmeasured anion, hypoalbuminemia decreases the expected anion gap. Without correction, a patient may appear to have a normal value even though a significant acid burden is present. The result is a better adjusted corrected anion gap, which is particularly useful in patients with chronic illness, inflammation, or fluid shifts.
The key practical lesson is that the anion gap should not be interpreted in isolation. The number is best viewed together with bicarbonate, pH, and carbon dioxide as part of a broader acid-base assessment. That integrated approach boosts confidence and reduces the risk of missing a clinically important metabolic disorder.
High Anion Gap Acidosis
Elevated anion gap metabolic acidosis develops when unmeasured acids build up in the bloodstream. This is considered one of the most important patterns detected by the anion gap because it can identify serious illness early. In many cases, the anion gap is raised before the complete clinical picture becomes obvious, making it a valuable marker of developing metabolic acidosis.
Frequent causes include lactic acidosis, ketoacidosis, and uremia. Lactic acidosis can occur when tissue perfusion is impaired or oxygen utilization is disrupted, leading to accumulated lactate. Ketoacidosis occurs when ketones rise, often in states of insulin deficiency or prolonged starvation. Uremia reflects holding back of acids and other waste products when kidney function is severely reduced.
From an interpretation standpoint, a high-gap disorder often produces a decreased bicarbonate level and a reduced pH. The respiratory system may respond by lowering the partial pressure of carbon dioxide through increased ventilation. That compensation can partly reduce acidemia, but it does not remove the underlying metabolic problem. This is anion gap with K calculator why using blood gas analysis alongside the anion gap strengthens diagnostic accuracy.
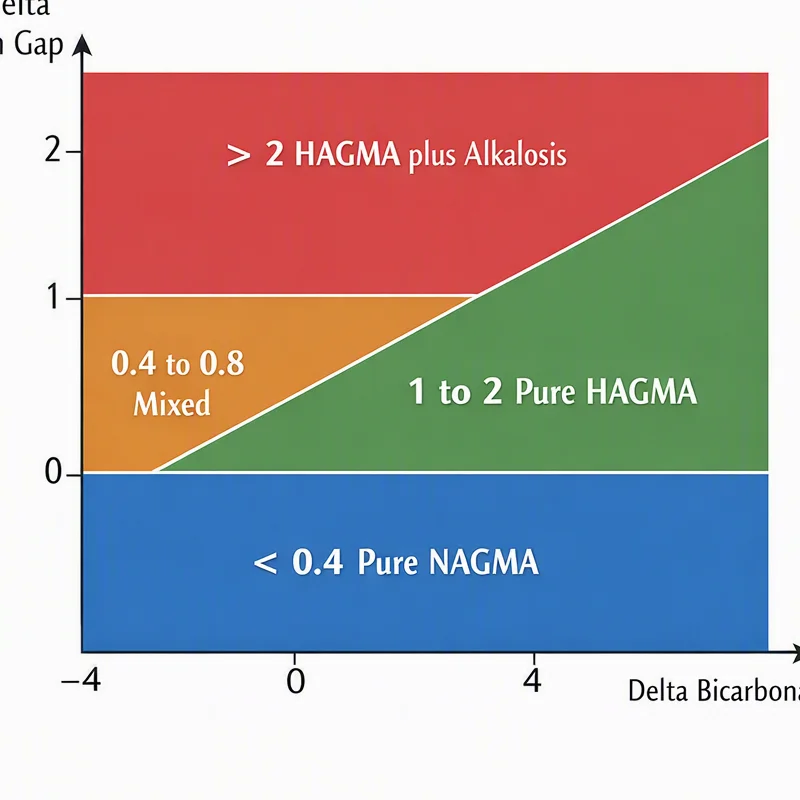
High-gap metabolic acidosis can also coexist with other acid-base disorders. For example, a patient may have a high-gap process and a simultaneous metabolic alkalosis or respiratory disorder. In these cases, the anion gap calculator is a starting point, not the final answer. Careful review of the overall acid-base balance is required to avoid missing a mixed disorder.
Typical Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis is also called chloride-rich acidosis. With this pattern, bicarbonate falls but chloride rises enough to keep the overall gap within the expected reference interval. This finding may still reflect a significant acid-base problem even though the anion gap itself is not elevated.
One common cause is bicarbonate loss. The body loses base, and chloride increases as a compensatory change. This may happen with gastrointestinal losses such as diarrhea, where bicarbonate-rich fluid is depleted. In the appropriate clinical setting, the combination of low bicarbonate and high chloride points toward this pattern rather than a high-gap disorder.
Another key cause is renal tubular acidosis, in which the kidneys fail to properly acidify urine or reclaim bicarbonate. This results in a persistent acidotic state despite a normal anion gap. Since the mechanism is different from high-gap acidosis, the treatment approach may also differ. This is why differentiating these entities matters anion gap clinical significance in clinical interpretation.
Normal-gap metabolic acidosis is a good example of why the anion gap calculator should be used together with blood gas analysis. A low pH and low bicarbonate may indicate metabolic acidosis, but the anion gap tells you whether the problem is due to unmeasured acids or to bicarbonate loss with chloride retention. This difference is central to the interpretation framework.
Typical Computational Missteps and Clinical Issues
Various issues can skew the apparent anion gap and lead to misinterpretation. Among the most common of the most common is laboratory error, which can arise from specimen handling, instrument variation, or recording errors. If the result does not fit the patient’s condition, the chemistry should be rechecked before making major conclusions.
Low albumin is another frequent pitfall. Since low albumin lowers the unmeasured anion pool, the anion gap may appear normal when it is not. This is one reason correction for albumin is so important. Without it, a major acid load can be missed, especially in inpatient or severely ill patients.
Free calcium and other electrolyte shifts can also alter the broader acid-base environment. While they do not directly define the anion gap, they may influence the overall clinical picture and contribute to confusion if the analysis focuses only on one number. Detailed review of the electrolyte panel helps reduce this risk.
A further major pitfall is relying on the anion gap without considering pH and carbon dioxide. A calculated value may be useful, but if the patient has a respiratory disorder or mixed acid-base pattern, the final conclusion can be misleading. Good interpretation uses the anion gap calculator as one element of a larger diagnostic tool, not as a replacement for blood gas analysis.
Finally, reference interval differences between laboratories can produce seemingly different results. A result that seems slightly elevated in one setting may be normal in another depending on the analyzer, method, and reporting conventions. Understanding the local reference range is important for sound clinical interpretation.
An FAQ on Anion Gap and Blood Gases
How do you calculate the anion gap from blood gas readings?
You generally never calculate the anion gap from the blood gas alone. The anion gap calculator relies on serum sodium, serum chloride, and bicarbonate from the chemistry panel. Blood gas analysis includes pH and partial pressure of carbon dioxide so you can assess the acid-base disorder more fully. If the blood gas reports a bicarbonate value, it can help with context, but the standard calculated value is still based on serum electrolytes.
Which is the normal anion gap range in adults?
The normal range varies with the laboratory technique and whether potassium is included. Many laboratories list a standard anion gap in the mid-teens, but the exact range should always be checked against the local report. The most important step is to compare the result with the lab’s own interval rather than using a universal cutoff.
Why do you adjust the anion gap for albumin?
Correction for albumin is required because albumin in serum is a major unmeasured negatively charged ion. In cases of low albumin, the anion gap may appear deceptively normal even when an increase in acid is present. The adjusted anion gap improves detection of hidden acidosis and provides a better estimate of the overall acid-base state.
Can blood gas analysis show metabolic acidosis by itself?
Blood gas analysis can often suggest metabolic acidosis by revealing a low pH and low bicarbonate, but it does not always explain the cause. The anion gap helps separate between high anion gap metabolic acidosis and normal anion gap metabolic acidosis. Combining both together offers a better clinical interpretation framework than blood gas alone.
What causes a high anion gap in clinical interpretation?
Frequent sources include lactic acidosis, ketoacidosis, and uremia. Such conditions cause anion gap elevation by adding unaccounted-for acids to the blood. When the anion gap is high, the result should be interpreted alongside pH, bicarbonate, and carbon dioxide so you can determine the degree of the acid-base disturbance and whether respiratory compensation is present.