What Is an Anion Gap Calculator?
An anion gap calculator is a simple medical tool used to calculate the variation between measured electrolytes in the blood, usually based on sodium, chloride, and bicarbonate. This resulting value helps evaluate whether there is an anion gap elevation suggestive of metabolic acidosis and related patterns of acid-base imbalance.
In basic serum chemistry interpretation, the calculator assists clinical interpretation by helping recognize whether there is excess unmeasured acid in the bloodstream. Because the body normally maintains tight acid-base balance, even small shifts in laboratory values can indicate an important metabolic derangement.
The main advantage of an anion gap calculator is its diagnostic utility. It does not establish a condition by itself, but it provides a quick way to screen for high anion gap metabolic acidosis, leading to further review of the patient’s symptoms, medications, and possible causes of acid accumulation.
In practice, the calculator is often used alongside the broader anion gap formula, other laboratory values, and the overall clinical picture. That includes looking for signs of electrolyte imbalance, dehydration, and acid-base disturbance that may require urgent evaluation.
What Is the Way the Anion Gap Is Related to Alcoholic ketoacidosis
Alcoholic ketoacidosis is a type of metabolic emergency that can arise after intense alcohol consumption, poor intake, and ongoing vomiting. The condition is defined by elevated ketone production, especially when the body moves away from glucose use and into fat metabolism. This causes the buildup of acidic ketones, including beta-hydroxybutyrate, which can raise the anion gap.
In alcoholic ketoacidosis, the blood often shows ketonemia with elevated amounts of ketones, but the pattern may be hard to detect if only urine ketones are checked. Beta-hydroxybutyrate is especially crucial because it is frequently the primary ketone in this condition. As these acids gather, they consume bicarbonate, reducing bicarbonate and contributing to metabolic acidosis.
This is why the anion gap calculator is so valuable in this setting. A high value can support suspicion for high anion gap metabolic acidosis, especially when combined with the patient’s history, volume status, and other laboratory findings. It can also be used to separate alcoholic ketoacidosis from other causes of acidosis that may appear alike at first glance.
Alcoholic ketoacidosis often occurs in the setting of volume depletion, poor oral intake, and ongoing vomiting. Those factors can amplify acid-base changes and make interpretation more complex. In some cases, the patient may have a mixed acid-base disorder, meaning more than one process is affecting the final pH.
How to Work Out the Anion Gap
The usual approach to determining the anion gap uses sodium, chloride, and bicarbonate. The standard calculation is:
Anion gap = sodium - (chloride + bicarbonate)
These results are usually taken from a basic metabolic panel or other serum chemistry panel. A elevated result suggests that unmeasured anions may be present in the blood, which is why the calculator is valuable for evaluating acid-base disorders.
Albumin also plays a role because it is a major unmeasured anion. When albumin is low, the measured anion gap can appear falsely normal or only mildly elevated. For that reason, lab result interpretation should consider whether an albumin-corrected anion gap is needed.
To use the calculator well, it helps to review each component carefully:
- Sodium represents the main measured cation in the formula. Chloride and bicarbonate are the main measured anions included in the calculation. Albumin changes the expected baseline and may change the interpretation.
Because minor changes in these laboratory values can shift the result, clinical interpretation should never rely on the number alone. A patient with alcoholic ketoacidosis may have a markedly abnormal anion gap even before severe pH changes are obvious.
Anion Gap Formula and Albumin Correction
The anion gap formula is simple, but assessment becomes less straightforward when albumin is low. Since hypoalbuminemia reduces the baseline anion gap, the uncorrected result may underestimate the true degree of acid-base disturbance.
That is why an albumin-corrected anion gap is often important. Accounting for albumin enhances the corrected anion gap estimate and can identify a clinically important gap that would otherwise be missed. This is important in patients with poor nutrition, chronic illness, or heavy alcohol use, where low albumin may be common.
A typical reference range for the anion gap varies depending on the laboratory method and whether potassium is included in the formula. The specific cutoffs can change by institution, so interpretation should always use the local reference range rather than assuming one anion gap clinical significance universal normal value.
In alcoholic ketoacidosis, albumin correction can be especially helpful because the patient may have multiple contributors to acid-base imbalance. A low albumin level may mask the severity of the high anion gap metabolic acidosis, making the corrected result more informative for clinical interpretation.
Key point: A normal-looking anion gap does not always exclude a significant acid-base disorder if albumin is low or if a mixed process is present.
Common Test Results in Alcoholic Ketoacidosis
Alcoholic ketoacidosis often creates a recognizable pattern of laboratory findings, though not every patient shows the same presentation. The core abnormality is typically elevated beta-hydroxybutyrate, which reflects active ketone production and helps support the diagnosis of ketonemia.
Glucose may be low, normal, or only slightly elevated. This can distinguish alcoholic ketoacidosis from diabetic ketoacidosis, where glucose is commonly much higher. However, overlap can occur, so glucose alone should not be used as the single discriminator.
Lactate may also be increased, especially if there is reduced perfusion, volume depletion, or impaired metabolism. That means some patients have both ketoacidosis and lactic acidosis, which can deepen the high anion gap. Lactate elevation does not exclude alcoholic ketoacidosis; it may simply add another layer of acid accumulation.
These findings Browse this site may include:
- Elevated beta-hydroxybutyrate Evidence of ketonemia Reduced bicarbonate High anion gap Variable glucose level Possible lactate elevation
The mix of these laboratory values strengthens the diagnosis, but the clinical context remains essential. Symptoms such as vomiting, poor intake, and recent alcohol cessation are especially important in recognizing the underlying metabolic derangement.
How to Read Output Carefully
Safe assessment of the anion gap requires looking beyond the calculator result and considering the entire acid-base picture. A patient may have a high anion gap and still have a near-normal pH if another process is also present. That is the hallmark of a mixed acid-base disorder.
For example, vomiting can cause metabolic alkalosis from loss of gastric acid while alcoholic ketoacidosis produces metabolic acidosis. The net pH may look less abnormal than expected. Because of that, a normal or only slightly abnormal pH should not override other evidence of a serious acid-base disturbance.
An arterial blood gas can help determine whether there is true acidemia, compensation, or an additional respiratory component. Blood gas data, together with serum chemistry, improves lab result interpretation and helps identify the full pattern of metabolic acidosis.
The osmolar gap is another important piece of information when the diagnosis is uncertain. An elevated osmolar gap may raise concern for toxic alcohol ingestion, especially if the history is unclear. In that setting, the anion gap calculator helps with differential diagnosis, but it should be used as part of toxin screening and broader evaluation rather than as a standalone answer.
Clinical interpretation is safest when all of the following are considered together:
- Clinical signs and history Serum chemistry results Arterial blood gas Albumin level Osmolar gap Possible mixed acid-base disorder
Common Causes of High Anion Gap
Alcoholic ketoacidosis is a cause of high anion gap metabolic acidosis, but it is only one possibility. An elevated gap reflects acid accumulation from various causes, and the differential diagnosis should remain open.
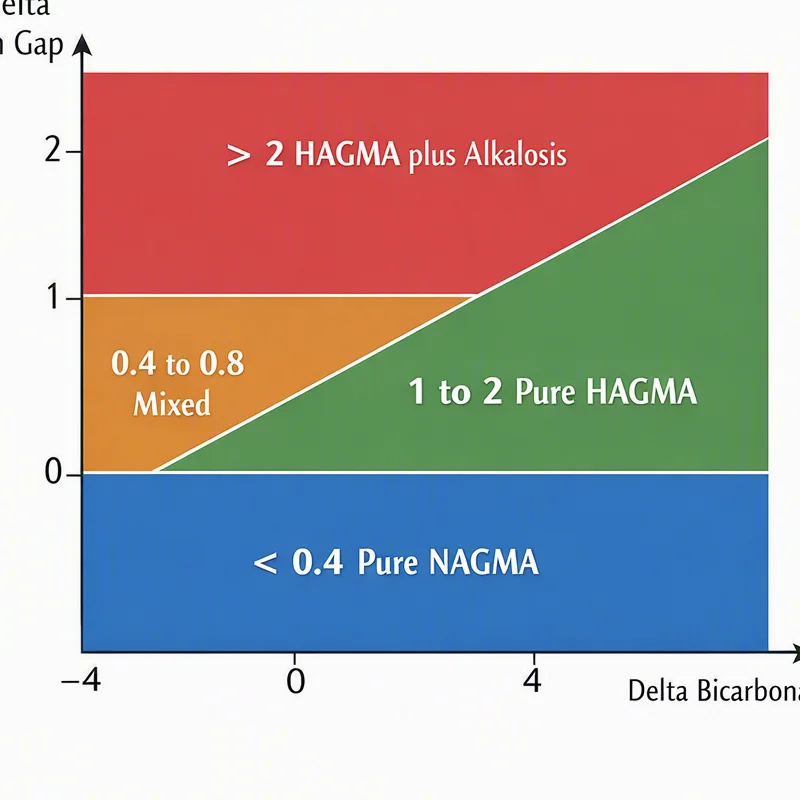
Notable causes include methanol poisoning, lactic acidosis, uremia, and diabetic ketoacidosis. Each of these can produce a comparable test pattern, though the history and accompanying findings often are different.
In toxic cases, toxic alcohol ingestion may also create a high anion gap and an osmolar gap, especially at first. This overlap is why careful interpretation matters. If toxic ingestion is suspected, immediate assessment and toxin screening may be needed.
Other contributors may include renal failure, severe infection, shock, and other forms of metabolic acidosis. The anion gap calculator helps identify the abnormality, but the next step is determining the underlying cause.
For a practical differential diagnosis, clinicians often compare patterns such as:
- Acid buildup driven by ketones in alcoholic ketoacidosis Marked hyperglycemia in diabetic ketoacidosis Increased lactate in lactic acidosis Kidney retention of acids in uremia Possible changes in the osmolar gap with methanol or other toxic alcohol ingestion
When to Seek Immediate Medical Attention
Alcoholic ketoacidosis can turn dangerous fast, especially when it is combined with ongoing vomiting, dehydration, or impaired mental status. Symptoms may start with nausea and abdominal discomfort, then advance to weakness, tachycardia, and confusion.
Throwing up and volume depletion are especially concerning because they intensify volume depletion and can intensify the acid-base disturbance. A rapid heartbeat, or tachycardia, may signal significant physiologic stress or dehydration.
Altered mental status is a major warning sign and should warrant urgent evaluation. This can reflect severe metabolic derangement, poor perfusion, hypoglycemia, toxic ingestion, or another medical emergency. If symptoms are severe or worsening, immediate medical care is needed.
People with suspected alcoholic ketoacidosis should not rely on a calculator result alone. A high anion gap, low bicarbonate, ketonemia, or abnormal arterial blood gas can suggest a condition that needs urgent treatment, including fluids, glucose, electrolyte correction, and close monitoring.
Urgent evaluation is needed if there is:
- Repeated vomiting Severe dehydration Tachycardia or weakness Confusion Possible toxic alcohol exposure Increasing acid-base imbalance
Common Questions About Anion Gap Calculator and Alcoholic Ketoacidosis
What is an anion gap calculator used for in alcoholic ketoacidosis?
An anion gap calculator is helpful for estimating the anion gap from routine lab values and support the detection of high anion gap metabolic acidosis. In alcoholic ketoacidosis, it may help confirm the diagnosis when ketones, low bicarbonate, and other laboratory values suggest acid accumulation. It is most useful for clinical interpretation, not as a standalone diagnosis.
How is the anion gap calculated from sodium, chloride, and bicarbonate?
The standard anion gap formula is sodium - (chloride + bicarbonate). This uses measured serum chemistry values to estimate the amount of unmeasured anions in the blood. If the result is above the local reference range, it suggests an acid-base disturbance such as metabolic acidosis.
Why does alcoholic ketoacidosis to result in a high anion gap?
Alcoholic ketoacidosis causes a high anion gap because the body creates excess acidic ketones, especially beta-hydroxybutyrate. These acids increase ketonemia, lower bicarbonate, and contribute to high anion gap metabolic acidosis. Vomiting, poor intake, and volume depletion can intensify the metabolic derangement more severe.
Does albumin help to correct the anion gap?
Yes, albumin should be used in interpretation because hypoalbuminemia can make the anion gap appear falsely low. An albumin-corrected anion gap can more accurately reflect the true acid-base status. This is especially important when interpreting labs in patients with malnutrition, ongoing disease, or suspected alcoholic ketoacidosis.
What else can cause a high anion gap besides alcoholic ketoacidosis?
Other common causes include diabetic ketoacidosis, lactic acidosis, uremia, and toxic alcohol ingestion such as methanol. These conditions can overlap in symptoms and laboratory findings, so the anion gap calculator should be used as part of a wider differential diagnosis and clinical evaluation.