Understanding the Anion Gap?
The anion gap is a calculated number that helps assess the balance of charged particles in the blood. It is derived from common electrolytes measured in a blood test, especially sodium, chloride, and bicarbonate. Because the body maintains acid-base balance through carefully controlled chemistry, the anion gap can serve as a helpful diagnostic clue when something is off in the body’s serum electrolytes.
At a simple level, the anion gap represents the discrepancy between the main measured cations and negative ions in the blood. Since not all ions are directly measured in routine blood chemistry, the gap helps suggest the presence of unmeasured anions. That is why it is often used in lab result interpretation and overall lab test interpretation when evaluating a metabolic disorder or electrolyte imbalance.
Doctors often review the anion gap as part of a blood chemistry panel or electrolyte panel. It is not a diagnosis by itself, but it can indicate conditions affecting acid-base status and overall clinical significance.
How the Anion Gap Calculator Works
An anion gap calculator uses specific lab values from a blood test and applies a simple formula to produce a result. The calculator is designed to help you calculate anion gap rapidly and consistently using the values reported in a standard lab report.
Most calculators request three main inputs: serum sodium, serum chloride, and serum bicarbonate. These are usually listed on an electrolyte panel or broader blood chemistry report. Once entered, the calculator subtracts chloride and bicarbonate from sodium to determine the gap.
The output can help identify whether the result fits a normal anion gap, a high anion gap, or a low anion gap. That classification matters because it informs the next step in results analysis. A high value often suggests excess acids or unmeasured anions, while a low value can point to protein abnormalities, especially changes in albumin.
In practical use, the calculator is only one part of medical interpretation. The result must be considered alongside symptoms, the full blood chemistry panel, and other tests that help explain the underlying cause.
Explaining the Anion Gap Formula
The standard anion gap formula is written as:
Na - (Cl + HCO3)
In this formula, Na means sodium, Cl means chloride, and HCO3 stands for bicarbonate. This is the heart of the anion gap calculation, and it serves as the basis of every reliable anion gap calculator.
To grasp the calculation steps, consider a lab report with these values:
- Na = 140 Cl = 102 HCO3 = 24
First off, add chloride and bicarbonate: 102 + 24 = 126. After that subtract that sum from sodium: 140 - 126 = 14. Here, the anion gap is 14.
This straightforward computation reflects the relationship between measured ions and the body’s hidden electrical balance. Because not every ion appears on routine labs, the result gives insight into serum electrolytes and can help identify an underlying metabolic acidosis or other acid-base disturbance.
Even though the formula is simple, the interpretation is where the real value lies. A number on its own is less meaningful than the pattern it creates with other clinical data.
Expected Anion Gap Range and Reference Values
The standard range for anion gap can differ by laboratory because different methods and instruments may produce slightly different results. For this reason it is important to check the lab’s reference range or normal interval rather than relying on a single universal cutoff.
In many settings, a typical result falls within a narrow range that reflects expected test values for sodium, chloride, and bicarbonate. However, the exact numbers depend on the laboratory’s testing method, the patient’s serum albumin, and whether the result has been adjusted using correction for albumin.
Serum albumin is a major negatively charged protein in blood, and it influences the anion gap significantly. If albumin is low, the anion gap may appear lower than expected even when the underlying acid-base picture is more complicated. For that reason, clinicians often consider a adjusted anion gap when albumin is abnormal.
Because lab-specific cutoffs are not the same, the best way to judge a value is to compare it with the laboratory’s stated reference interval and interpret it in the full context of the patient’s blood chemistry and symptoms. A “normal” result does not always rule out disease, and an “abnormal” result does not always mean a serious problem.
What High Anion Gap Suggests
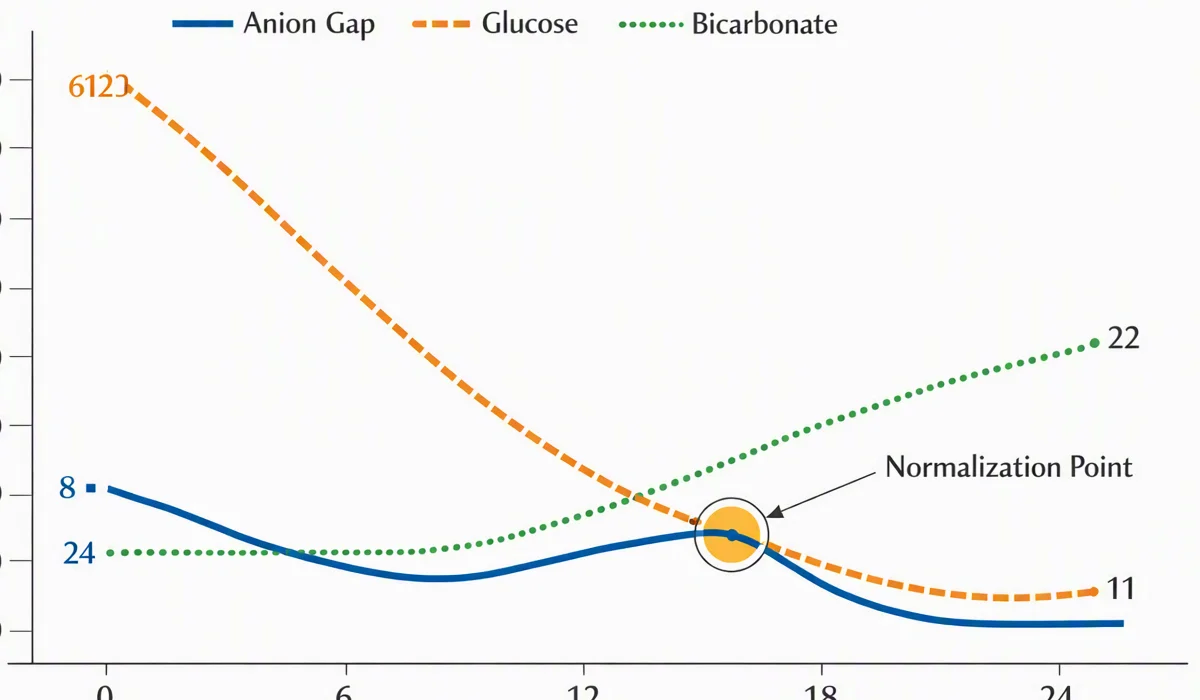
A high anion gap usually suggests that more acid or unmeasured anions are found in the blood. One major clinical associations is metabolic acidosis, a condition in which the body has excess acid or is unable to clear acid well.
Common causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactic acid builds up when tissues do not get enough oxygen or when metabolism is altered. In ketoacidosis, acid-producing ketones build up, often in settings such as uncontrolled diabetes, prolonged fasting, or heavy alcohol use. In renal failure, the kidneys cannot clear acids efficiently, leading to a increasing gap.
A high result is not a diagnosis by itself. It is a diagnostic clue that should lead to further evaluation into the patient’s acid-base status, symptoms, medications, and recent illness. The broader pattern on the blood chemistry panel often helps reveal the answer to understanding the cause.
Other findings may support the interpretation. For example, low bicarbonate on the electrolyte panel points to a metabolic acid problem. If the anion gap is high and the patient has signs of dehydration, infection, poor tissue oxygenation, or uncontrolled diabetes, the result becomes more concerning. Careful results analysis is important before drawing conclusions.
Understanding Low Anion Gap Indicates
A low anion gap is rarer than a high one, but it can still be of clinical significance. The most frequent reason is hypoalbuminemia, meaning the blood has too little albumin. Since albumin is a major unmeasured anion, a decreased level can reduce the calculated gap.
In some cases, a low result points to a lab error. That is why rechecking the test or reviewing the sample handling process is often important before assuming a disease process. Small measurement issues with sodium, why is AG elevated chloride, or bicarbonate can affect the final number.
A persistently low anion gap may also be seen in conditions such as multiple myeloma, where abnormal proteins affect the electrical balance in blood. In such cases, the low result may be a clue to an underlying protein disorder rather than a simple electrolyte issue.
Low values should be interpreted carefully because they can be misleading if albumin is not considered. This is where albumin correction becomes useful. Adjusting for albumin can uncover a hidden abnormality or show that the measured value is lower mainly because of protein loss. Either way, the low result deserves context.
How to Interpret Results Together with Other Lab Tests
An anion gap should not often stand alone. A full evaluation often includes an arterial blood gas, the complete electrolyte panel, and additional markers of kidney and metabolic function. Taken together, these tests help determine the patient’s acid-base balance and overall medical interpretation.
An arterial blood gas gives details on pH, carbon dioxide, and oxygenation. Used alongside the anion gap, it helps clarify whether there is metabolic acidosis, respiratory compensation, or a mixed disorder. This brings more depth to the lab test interpretation and improves diagnostic accuracy.
Albumin correction is especially important when the albumin level is abnormal. A corrected result may more closely represent the true anion gap formula result by accounting for the effect of low protein on the calculation. This is valuable in patients with chronic illness, malnutrition, inflammation, or liver-related protein changes.
Potassium can also be helpful, even though it is not always included in the basic formula. It plays a role in the overall electrolyte picture and may reveal a broader electrolyte imbalance. In addition, kidney markers and measures of renal function are essential when a high gap raises concern for impaired acid clearance or advanced disease.
Overall, the best interpretation comes from combining the number with symptoms, medication history, and all available blood chemistry data. That is the difference between a raw calculation and a clinically useful result.
Frequently Asked Concerns About Anion Gap Calculation
The FAQ here covers frequent concerns about anion gap calculation, the calculation process, and how to interpret the result in practical medical interpretation.
What is the formula for calculating anion gap?
The standard formula is Na - (Cl + HCO3). It uses serum sodium, serum chloride, and serum bicarbonate from a blood test to calculate the gap. This is the most common anion gap formula used in clinical practice and in an anion gap calculator.
What does a high anion gap indicate?
A high anion gap often suggests metabolic acidosis caused by extra acids or unmeasured anions. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result is a clue that more testing may be needed.
Can albumin change the anion gap result?
Yes. Albumin has a significant effect on the result because it is one of the main unmeasured anions in blood. A low albumin level can make the measured gap appear lower, which is why albumin correction and a corrected anion gap are often taken into account in interpretation.
What is considered a normal anion gap?
The normal anion gap depends on the lab’s reference range or reference interval. There is no single universal cutoff because lab values vary by method and instrument. The best approach is to compare the result with the laboratory’s reported range and the rest of the blood chemistry panel.
Why might an anion gap be low?
A low anion gap may occur because of hypoalbuminemia, lab error, or conditions such as multiple myeloma. Since low values can reflect measurement issues or protein changes, repeat testing and review of the full electrolyte panel are often useful before making conclusions.
When used properly, an anion gap calculator helps simplify the work of detecting acid-base disorders and aid more accurate lab result interpretation. This number is only the beginning; the real advantage comes from grasping the formula, verifying the reference range, and reading the result with the full clinical picture.